Buspar
In brief
- In our pharmacy, you can buy Buspar without a prescription, with delivery across the United Kingdom in 9–21 days. Discreet and anonymous packaging is available.
- Buspar (buspirone) is used to treat generalised anxiety disorder and as an adjunct in some mood disorders; it is a non‑benzodiazepine anxiolytic that acts mainly as a 5‑HT1A serotonin receptor partial agonist (modulating serotonergic neurotransmission) with additional dopaminergic effects, producing anxiolysis without typical benzodiazepine sedation or dependence.
- The usual dose for adults starts at 5 mg two to three times daily, typically titrated to 15–30 mg/day given in two or three divided doses; the maximum recommended daily dose is 45 mg, with increases of about 5 mg every 2–3 days as needed.
- The form of administration is oral tablets available in 5 mg and 10 mg strengths.
- Initial improvements may be noticed within 1–2 weeks, but maximum therapeutic effect often requires 2–4 weeks of regular treatment.
- Each dose provides symptomatic coverage for several hours (commonly about 6–8 hours), so buspirone is usually taken two or three times daily; sustained clinical benefit accrues with continued use.
- Do not consume alcohol while taking buspar—alcohol can increase dizziness, drowsiness and other adverse effects and impair safe functioning.
- Most common side effects: dizziness, headache, nausea, nervousness/restlessness, lightheadedness, insomnia, fatigue and dry mouth; these are usually mild and transient.
- Would you like to try Buspar without a prescription?
Legal status and availability in the UK
Buspar is a prescription-only medicine (POM) in the UK.
In our online pharmacy, Buspar is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Basic Buspar information
- INN (international nonproprietary name): buspirone
- Brand names available in the United Kingdom: Buspar; buspirone generics
- ATC code: N05BE01
- Forms and dosages: tablets 5 mg and 10 mg
- Manufacturers in the United Kingdom: Pfizer (originator), Teva, Mylan, Apotex and others
- Registration status in the United Kingdom: licensed for anxiety
- OTC / Rx classification: Prescription-only medicine (POM)
Buspar (INN: buspirone) sits in a specific niche as a non‑sedating, non‑benzodiazepine anxiolytic used mainly for Generalised Anxiety Disorder (GAD).
It is commonly considered by GPs for people who want daytime functioning without sedation, those with prior substance misuse and older adults.
Common concerns are the delayed onset of effect (often 2–4 weeks) and the need for regular dosing rather than PRN use. Frequent questions include “Is it addictive?”, “How long until it works?” and “Can I take it with other medicines?”.
Product snapshot: names, forms and packaging
What is supplied in the UK
The INN is buspirone, and Buspar is supplied in the UK alongside generics.
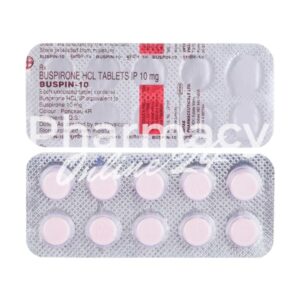
Tablets are the only marketed form, in 5 mg and 10 mg strengths, usually sold in blister packs. Some packs have score marks to aid splitting for smaller doses.
No extended‑release, injectable or alternative release products are marketed for buspirone.
Indications and typical use cases
Licensed uses and common off‑label considerations
Where does buspirone fit in routine prescribing?
Primary licensed indication is Generalised Anxiety Disorder and this is its standard role in NHS care and private practice.
Buspirone is not suitable for acute panic attacks or as a rescue medication because onset is slower than sedating agents.
Typical patient suitability includes those needing long‑term, non‑sedating anxiolytic therapy, people at risk of benzodiazepine dependence and those requiring adjunctive therapy with antidepressants.
Off‑label uses seen in practice include augmentation in depression, adjunctive therapy for PMDD and studied roles in withdrawal syndromes, though evidence is variable and prescriber guidance is required.
Expect onset to take 2–4 weeks and that treatment duration is decided by clinical response, often continuing for weeks to months.
- Licensed
- Generalised Anxiety Disorder (GAD) — established indication.
- Off‑label
- Adjunct in depression, PMDD support, studied in withdrawal settings — consult prescriber and rely on evidence before use.
Not for panic or PRN use: buspirone is not a rescue medication for immediate relief; discuss alternatives with the prescriber for acute symptoms.
Dosage, titration and administration practicalities
Typical regimens, titration schedule and missed‑dose guidance
How should patients take buspirone safely and effectively?
Typical adult starting dose is 5 mg two to three times daily, titrating by about 5 mg every 2–3 days under prescriber supervision.
Usual maintenance is 15–30 mg per day in two or three divided doses, and the maximum licensed dose is 45 mg per day.
Titration should be supervised by the prescriber and patients should be told that effects accumulate over 2–4 weeks.
Tablets are swallowed with water and should be taken consistently in relation to meals for steady blood levels.
Grapefruit and strong CYP3A4 inhibitors can increase buspirone levels and are discussed in interactions guidance.
If a dose is missed, take it as soon as remembered unless close to the next dose; do not double up to make up a missed dose.
In elderly patients and those with hepatic or renal impairment apply “start low, go slow” and monitor for dizziness or increased effects.
| Timepoint | Dose |
|---|---|
| Initial | 5 mg two to three times daily |
| Titration | Increase ~5 mg every 2–3 days as needed |
| Typical maintenance | 15–30 mg daily in divided doses |
| Maximum | 45 mg daily |
Pharmacology and how buspirone works
Mechanism summary and practical implications for patients
What does buspirone do in the brain and what does that mean for patients?
Buspirone is classified under ATC N05BE01 as a non‑benzodiazepine anxiolytic with a distinct pharmacological profile.
It has partial agonist activity at 5‑HT1A receptors and modulates serotonergic and some dopaminergic tone, which underpins its anxiolytic effects.
This mechanism explains why buspirone does not produce the sedation, muscle relaxation or anticonvulsant effects seen with benzodiazepines.
Practical implications include a lower risk of physical dependence, less sedation and minimal respiratory depression risk compared with benzodiazepines.
The onset is slower than with benzodiazepines, so buspirone should not be used for immediate relief.
| Feature | Buspirone | Benzodiazepines |
|---|---|---|
| Onset | Days–weeks | Minutes–hours |
| Dependence risk | Low | Higher |
| Sedation | Minimal | Marked |
Safety, contraindications and red flags
Absolute and relative contraindications
Who must not take buspirone?
Absolute contraindications are known hypersensitivity to buspirone or excipients and concomitant use with strong CYP3A4 inhibitors which can raise levels markedly.
Relative contraindications that require caution include moderate to severe hepatic or renal impairment, recent or concurrent MAOI therapy and frailty in elderly patients.
Before starting, tell the prescriber or pharmacist about current prescription and over-the-counter medicines, herbal products, liver and kidney disease, pregnancy or breastfeeding status and alcohol or substance misuse history.
Red‑flag symptoms requiring urgent review include signs of allergic reaction, severe dizziness, or symptoms suggesting serotonin syndrome when combined with other serotonergic medicines.
Seek advice from a prescriber for potent CYP3A4 inhibitors and contact your GP or NHS 111 for urgent symptoms.
Side effects, prevalence and mitigation strategies
Common, less common and management advice
What side effects do patients commonly report?
Common adverse effects include dizziness, headache, nausea, nervousness, lightheadedness, restlessness, insomnia, fatigue and dry mouth; most are mild and transient.
Because buspirone is generally non‑sedating and not habit‑forming, these features are often highlighted compared with benzodiazepines.
Practical mitigation advice: take with food to reduce nausea, rise slowly from sitting to reduce dizziness and avoid driving until the individual knows how the medicine affects them.
If insomnia occurs, consider dosing adjustments (avoid late evening doses) and discuss alternatives with the prescriber if symptoms persist.
Rare but serious reactions require immediate medical attention and include severe allergic responses or profound dizziness affecting safety.
| Side effect | Frequency | Tips |
|---|---|---|
| Nausea | Common | Take with food; small, frequent meals. |
| Dizziness / lightheadedness | Common | Avoid driving until stable; stand up slowly. |
| Insomnia | Common | Avoid evening dosing; review with prescriber if persistent. |
| Dry mouth | Common | Stay hydrated; sugar‑free gum or lozenges. |
Most effects settle over days; report persistent or severe symptoms for dose review or switching therapy.
Drug interactions
CYP3A4, MAOIs and serotonergic combinations
Which interactions demand immediate attention?
Strong CYP3A4 inhibitors such as certain azole antifungals, macrolide antibiotics and some protease inhibitors can substantially increase buspirone blood levels and require prescriber review and possible dose reduction.
Co‑administration with MAO inhibitors is a significant concern and should be avoided due to risk of adverse effects.
Combining buspirone with SSRIs or SNRIs increases serotonergic load and vigilance for serotonin syndrome is required.
OTC and herbal interactions include St John’s wort and other CYP modulators; patients should be counselled to declare herbal remedies.
Alcohol is not advised until the patient understands individual tolerance to buspirone effects even though buspirone is not a sedative in the benzodiazepine sense.
- High‑risk drugs: strong CYP3A4 inhibitors (e.g., ketoconazole, itraconazole), potent macrolides, certain HIV protease inhibitors.
- Serotonergic agents: SSRIs/SNRIs — monitor for agitation, hyperreflexia, fever and autonomic disturbance.
Special populations: elderly, pregnancy, children
Age, pregnancy, breastfeeding and renal or hepatic impairment
How should buspirone be handled in groups needing extra caution?
Children under 18: efficacy and safety not established and use is generally not recommended.
Elderly patients: start at lower doses and titrate slowly because of increased central nervous system sensitivity and fall risk; monitor closely for dizziness and sedation.
Hepatic and renal impairment: reduced clearance can increase effects so dose reduction and closer monitoring are advised.
Pregnancy and breastfeeding: data are limited; prescribers should perform individual risk–benefit assessments and consider UK reference sources such as the BNFC and specialist advice.
| Population | Recommended approach |
|---|---|
| Children (<18) | Not recommended; refer to paediatric specialist. |
| Elderly | Start low, titrate slowly; monitor for falls and CNS effects. |
| Hepatic or renal impairment | Consider dose reduction and increased monitoring. |
| Pregnancy and breastfeeding | Discuss risks/benefits with prescriber and specialist services. |
Not for children under 18: paediatric use is not established and specialist referral is required for younger patients.
Comparison with other anxiety treatments
When Buspar is preferred and when alternatives are chosen
How does buspirone compare to other anxiety treatments in practice?
Buspar is preferred when dependency risk or daytime sedation is a major concern, for example in patients with past benzodiazepine misuse or occupations requiring alertness.
Benzodiazepines remain the choice for rapid relief of acute anxiety, severe agitation or panic attacks due to their fast onset.
SSRIs are commonly first‑line for chronic GAD and comorbid depression; buspirone can be useful as an adjunct or where SSRI adverse effects limit use.
Hydroxyzine gives immediate sedating anxiolysis but carries daytime sedation and anticholinergic burden.
Pregabalin has evidence in some forms of anxiety but brings its own risk profile and monitoring needs.
| Attribute | Buspirone | Benzodiazepines | SSRIs |
|---|---|---|---|
| Onset | 2–4 weeks | Minutes–hours | Weeks |
| Dependence risk | Low | High | Low |
| Sedation | Minimal | Often marked | Variable |
Packaging, labelling and storage guidance
Labelling and stability tips
Tablets are normally packed in blister packs with clear strength markings, batch number and expiry date visible.
Store at controlled room temperature (around 20–25°C), avoid moisture and direct sunlight and keep in the original packaging to maintain stability.
Return unused medication to a pharmacy and do not flush tablets down the sink or toilet.
- Do: keep in original pack, store at room temperature, return unused packs to a pharmacy.
- Do not: expose to heat or damp environments; share medication with others.
Counselling points
Buspirone is for ongoing anxiety treatment; it is not for immediate relief and may take a few weeks to work.
It is taken regularly rather than as needed, usually two or three times daily.
Common transient effects (nausea, dizziness, headache) can be eased by taking tablets with food and avoiding driving until the effects are known.
Avoid potent CYP3A4 inhibitors and tell the prescriber about SSRIs, SNRIs or herbal products.
If you miss a dose, take it when you remember unless it is nearly time for the next dose; do not double up. In case of overdose seek immediate medical attention.
A check at 1–2 weeks for tolerability and a review at 4–6 weeks for efficacy are typical. For red-flag symptoms contact your GP or NHS 111.
Delivery across the United Kingdom
| City | Region | Delivery time |
|---|---|---|
| London | Greater London | 9–21 days |
| Birmingham | West Midlands | 9–21 days |
| Manchester | Greater Manchester | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Leeds | West Yorkshire | 9–21 days |
| Sheffield | South Yorkshire | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Bristol | South West England | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Newcastle Upon Tyne | North East England | 9–21 days |
| Nottingham | East Midlands | 9–21 days |
| Coventry | West Midlands | 9–21 days |
| Leicester | East Midlands | 9–21 days |