Buspar
In brief
- In our pharmacy, you can buy buspar without a prescription, with delivery across the United Kingdom in 5–14 days. Discreet and anonymous packaging is available.
- Buspar (buspirone) is used to treat generalized anxiety disorder and as an adjunct in some mood disorders; it is a non‑benzodiazepine anxiolytic that acts mainly as a 5‑HT1A serotonin receptor partial agonist (modulating serotonergic neurotransmission) with additional dopaminergic effects, producing anxiolysis without typical benzodiazepine sedation or dependence.
- The usual dose for adults starts at 7.5 mg twice daily (15 mg/day), typically titrated to 15–30 mg/day given in two or three divided doses; the maximum recommended daily dose is 60 mg, with increases of about 5 mg every 2–3 days as needed.
- The form of administration is oral tablets (film‑coated tablets/caplets) available commonly in 5 mg, 10 mg, 15 mg and 30 mg strengths.
- Initial improvements may be noticed within 1–2 weeks, but maximum therapeutic effect often requires 2–4 weeks of regular treatment.
- Each dose provides symptomatic coverage for several hours (commonly about 6–8 hours), so buspirone is usually taken two or three times daily; sustained clinical benefit accrues with continued use.
- Do not consume alcohol while taking buspar—alcohol can increase dizziness, drowsiness and other adverse effects and impair safe functioning.
- Most common side effec: dizziness, headache, nausea, nervousness/restlessness, lightheadedness, insomnia, fatigue and dry mouth; these are usually mild and transient.
- Would you like to try buspar without a prescription?
Market Realities & Patient Experiences With Buspar
Basic Buspar Information
- INN (International Nonproprietary Name): buspirone (Buspironum in Latin, Buspirona in Spanish/Portuguese/Italian, Буспирон in Cyrillic-based languages).
- Brand Names Available In United Kingdom: generics widely available (examples in Europe include Buspiron ratiopharm, Buspiron Teva, Bespar) and the originator BuSpar® is noted internationally; manufacturers supplying UK markets include Pfizer, TEVA, Mylan, Apotex, Ratiopharm and Sandoz.
- ATC Code: N05BE01.
- Forms & Dosages: tablets 5 mg, 10 mg, 15 mg and 30 mg; no injectables or extended‑release formulations marketed.
- Manufacturers In United Kingdom: supplied by global and regional manufacturers such as Pfizer (originator), TEVA, Mylan, Apotex, Torrent and Ratiopharm; European labels also include Sandoz, Krka and Stada.
- Registration Status In United Kingdom: prescription only and approved for anxiety in established markets.
- OTC / Rx Classification: Prescription (Rx‑only) in all established markets.
Who buys Buspar and why?
Buspar (INN: buspirone) sits in a specific niche as a non‑sedating, non‑benzodiazepine anxiolytic used mainly for Generalised Anxiety Disorder (GAD).
UK patients looking for daytime functioning without sedation, those with prior substance misuse or older adults are commonly referred to buspirone by GPs.
Typical routes to supply include NHS prescriptions, private prescriptions and e‑prescriptions filled at high‑street chains and regulated online pharmacies.
Common pain points raised by patients are the delayed onset of effect (often 2–4 weeks), the need for regular dosing rather than PRN use, and differences in cost between NHS provision and private purchase.
Availability across Boots, LloydsPharmacy and reputable online e‑pharmacies means substitution with generics is frequent.
Frequent consumer questions pharmacists answer include “Is it addictive?”, “How long until it works?” and “Can I take it with other medicines?”.
Pharmacist counselling and trust are major drivers of purchase decisions in the UK market.
Patient Personas:
- Older adult with GAD wanting to avoid daytime sedation and falls risk.
- Person with history of benzodiazepine dependence seeking a non‑habit forming option.
- Working professional needing daytime alertness while managing chronic anxiety.
- Patient intolerant of SSRI side effects using buspirone as adjunct or alternative.
Patient Journey Flowchart:
- Presentation to GP with anxiety symptoms.
- Assessment and decision (NHS or private prescriber) with consideration of history and comorbidity.
- Prescription issued (paper or e‑prescription).
- Dispensing at community pharmacy or online e‑pharmacy with pharmacist counselling.
- Follow‑up appointment at 2–6 weeks to review tolerability and efficacy.
Product Snapshot: Names, Forms And Packaging
What’s Sold In The UK And Common International Equivalents
What should a customer expect to find on the shelf or online when searching for buspar?
INN is buspirone and the most recognised international brand is BuSpar® in the United States, with generics commonly supplied in the UK and Europe.
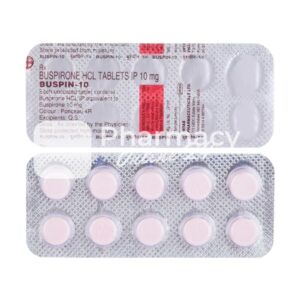
Tablets are the only marketed form and usual strengths are 5 mg, 10 mg, 15 mg and 30 mg, sold in blister packs (typically 10–30 tablets) or bottles (commonly 30–100 tablets).
Some European packs include score marks to aid splitting for smaller doses.
No extended‑release, injectable or alternative release products are marketed for buspirone.
Pharmacists should list MHRA‑approved generics and manufacturers on the product page; common suppliers include Sandoz, TEVA, Mylan and Apotex.
International language variants that help verification include Buspironum and Buspirona alongside the Cyrillic form Буспирон.
The ATC code N05BE01 should appear on clinical categorisation pages to support product classification.
| Brand / Manufacturer | Strength | Pack Size |
|---|---|---|
| BuSpar® (Pfizer) | 5 mg, 10 mg, 15 mg, 30 mg | Bottles 30–100; blister 10–30 |
| Buspiron Teva / TEVA (generic) | 5 mg, 10 mg, 30 mg | Blister 10–30 |
| Buspiron ratiopharm / Ratiopharm | 5 mg, 10 mg, 30 mg | Blister 10–30 |
| Mylan / Sandoz generics | 5 mg, 10 mg, 15 mg, 30 mg | Bottles 30; blister 10–30 |
Thumbnail gallery: display front and back artwork of each pack and show any score marks in the product images for patients who may split tablets.
Indications And Typical Use Cases
Licensed Uses And Common Off‑Label Considerations
Where does buspirone fit in routine prescribing?
Primary licensed indication is Generalised Anxiety Disorder and this is its standard role in NHS care and private practice.
Buspirone is not suitable for acute panic attacks or as a rescue medication because onset is slower than sedating agents.
Typical patient suitability includes those needing long‑term, non‑sedating anxiolytic therapy, people at risk of benzodiazepine dependence and those requiring adjunctive therapy with antidepressants.
Off‑label uses seen in practice include augmentation in depression, adjunctive therapy for PMDD and studied roles in withdrawal syndromes, though evidence is variable and prescriber guidance is required.
On a product page, include clear “Who It’s For” guidance and recommend GP or pharmacist consultation if the diagnosis or comorbidity is unclear.
Expect onset to take 2–4 weeks and that treatment duration is decided by clinical response, often continuing for weeks to months.
- Licensed
- Generalised Anxiety Disorder (GAD) — established indication.
- Off‑Label
- Adjunct in depression, PMDD support, studied in withdrawal settings — consult prescriber and rely on evidence before use.
Buspirone is not a rescue medication for immediate relief; discuss alternatives with the prescriber for acute symptoms.
Dosage, Titration And Administration Practicalities
Typical Regimens, Titration Schedule And Missed‑Dose Guidance
How should patients take buspirone safely and effectively?
Typical adult starting dose is 7.5 mg twice daily, titrating by about 5 mg every 2–3 days under prescriber supervision.
Usual maintenance is 15–30 mg per day in two or three divided doses, and the maximum licensed dose is 60 mg per day.
Titration should be supervised by the prescriber and patients should be told that effects accumulate over 2–4 weeks.
Tablets are swallowed with water and should be taken consistently in relation to meals for steady blood levels.
Grapefruit and strong CYP3A4 inhibitors can increase buspirone levels and are discussed in interactions guidance.
Missed dose advice for labels: take as soon as remembered unless close to the next dose; do not double up to make up a missed dose.
In elderly patients and those with hepatic or renal impairment apply “start low, go slow” and monitor for dizziness or increased effects.
| Timepoint | Dose |
|---|---|
| Initial | 7.5 mg twice daily |
| Titration | Increase ~5 mg every 2–3 days as needed |
| Typical Maintenance | 15–30 mg daily in divided doses |
| Maximum | 60 mg daily |
Provide a printable dosing schedule graphic on pack pages for patient leaflets and a pill‑timer visual for adherence support.
Pharmacology & How Buspirone Works (Brief, Actionable)
Mechanism Summary And Practical Implications For Patients
What does buspirone do in the brain and what does that mean for patients?
Buspirone is classified under ATC N05BE01 as a non‑benzodiazepine anxiolytic with a distinct pharmacological profile.
It has partial agonist activity at 5‑HT1A receptors and modulates serotonergic and some dopaminergic tone, which underpins its anxiolytic effects.
This mechanism explains why buspirone does not produce the sedation, muscle relaxation or anticonvulsant effects seen with benzodiazepines.
Practical implications include a lower risk of physical dependence, less sedation and minimal respiratory depression risk compared with benzodiazepines.
Patients must be advised the onset is slower than benzodiazepines and should not be used for immediate relief.
| Feature | Buspirone | Benzodiazepines |
|---|---|---|
| Onset | Days–weeks | Minutes–hours |
| Dependence Risk | Low | Higher |
| Sedation | Minimal | Marked |
Reference MHRA and NHS leaflets for clinicians and include a simple receptor‑action infographic for patient pages.
Safety, Contraindications And Red Flags
Absolute And Relative Contraindications With Patient Checks
Which patients must not receive buspirone and what should pharmacists screen for?
Absolute contraindications are known hypersensitivity to buspirone or excipients and concomitant use with strong CYP3A4 inhibitors which can raise levels markedly.
Relative contraindications that require caution include moderate to severe hepatic or renal impairment, recent or concurrent MAOI therapy and frailty in elderly patients.
Pharmacist safety checks should cover current prescription and OTC medicines, herbal products, liver and kidney disease, pregnancy or breastfeeding status and alcohol or substance misuse history.
Red‑flag symptoms requiring urgent review include signs of allergic reaction, severe dizziness, or symptoms suggesting serotonin syndrome when combined with other serotonergic medicines.
Action steps at the counter: stop supply if acute allergic signs present, seek prescriber advice for potent CYP3A4 inhibitors and refer to GP or NHS 111 for urgent symptoms.
- Checklist For Supply: medication list, hepatic/renal history, pregnancy/breastfeeding, substance misuse history.
- If In Doubt: contact the prescriber to discuss dose adjustment or alternative therapy.
Side Effects, Prevalence And Mitigation Strategies
Common, Less Common And Management Advice
What side effects do patients commonly report and how can pharmacists help?
Common adverse effects include dizziness, headache, nausea, nervousness, lightheadedness, restlessness, insomnia, fatigue and dry mouth; most are mild and transient.
Because buspirone is generally non‑sedating and not habit‑forming, these features are often highlighted compared with benzodiazepines.
Practical mitigation advice: take with food to reduce nausea, rise slowly from sitting to reduce dizziness and avoid driving until the individual knows how the medicine affects them.
If insomnia occurs, consider dosing adjustments (avoid late evening doses) and discuss alternatives with the prescriber if symptoms persist.
Rare but serious reactions require immediate medical attention and include severe allergic responses or profound dizziness affecting safety.
| Side Effect | Frequency | Pharmacist Tips |
|---|---|---|
| Nausea | Common | Take with food; small, frequent meals. |
| Dizziness / Lightheadedness | Common | Avoid driving until stable; stand up slowly. |
| Insomnia | Common | Avoid evening dosing; review with prescriber if persistent. |
| Dry Mouth | Common | Stay hydrated; sugar‑free gum or lozenges. |
Counselling lines: reassure patients most effects settle over days and to report persistent or severe symptoms for dose review or switching therapy.
Drug Interactions To Prioritise At The Counter
CYP3A4, MAOIs And Serotonergic Combinations
Which interactions demand immediate attention during screening?
Strong CYP3A4 inhibitors such as certain azole antifungals, macrolide antibiotics and some protease inhibitors can substantially increase buspirone blood levels and require prescriber review and possible dose reduction.
Co‑administration with MAO inhibitors is a significant concern and should be avoided due to risk of adverse effects.
Combining buspirone with SSRIs or SNRIs increases serotonergic load and vigilance for serotonin syndrome is required.
OTC and herbal interactions include St John’s wort and other CYP modulators; patients should be counselled to declare herbal remedies.
Alcohol is not advised until the patient understands individual tolerance to buspirone effects even though buspirone is not a sedative in the benzodiazepine sense.
- High‑risk drugs: strong CYP3A4 inhibitors (e.g., ketoconazole, itraconazole), potent macrolides, certain HIV protease inhibitors.
- Serotonergic agents: SSRIs/SNRIs — monitor for agitation, hyperreflexia, fever and autonomic disturbance.
Referral language: “This medicine may interact with X; please contact the prescriber to discuss dose adjustment or alternative therapy.”
Special Populations: Elderly, Pregnancy, Children
Age, Pregnancy/Breastfeeding And Renal/Hepatic Impairment Notes
How should buspirone be handled in groups needing extra caution?
Children under 18: efficacy and safety not established and use is generally not recommended.
Elderly patients: start at lower doses and titrate slowly because of increased central nervous system sensitivity and fall risk; monitor closely for dizziness and sedation.
Hepatic and renal impairment: reduced clearance can increase effects so dose reduction and closer monitoring are advised.
Pregnancy and breastfeeding: data are limited; prescribers should perform individual risk–benefit assessments and consider UK reference sources such as the BNFC and specialist advice.
| Population | Recommended Approach |
|---|---|
| Children (<18) | Not recommended; refer to paediatric specialist. |
| Elderly | Start low, titrate slowly; monitor for falls and CNS effects. |
| Hepatic/Renal Impairment | Consider dose reduction and increased monitoring. |
| Pregnancy/Breastfeeding | Discuss risks/benefits with prescriber and specialist services. |
Paediatric use is not established and specialist referral is required for younger patients.
Comparative Positioning Against Competitors
When Buspar Is Preferred And When Alternatives Win
How does buspirone compare to other anxiety treatments in practice?
Buspar is preferred when dependency risk or daytime sedation is a major concern, for example in patients with past benzodiazepine misuse or occupations requiring alertness.
Benzodiazepines remain the choice for rapid relief of acute anxiety, severe agitation or panic attacks due to their fast onset.
SSRIs are commonly first‑line for chronic GAD and comorbid depression; buspirone can be useful as an adjunct or where SSRI adverse effects limit use.
Hydroxyzine gives immediate sedating anxiolysis but carries daytime sedation and anticholinergic burden.
Pregabalin has evidence in some forms of anxiety but brings its own risk profile and monitoring needs.
| Attribute | Buspirone | Benzodiazepines | SSRIs |
|---|---|---|---|
| Onset | 2–4 weeks | Minutes–hours | Weeks |
| Dependence Risk | Low | High | Low |
| Sedation | Minimal | Often marked | Variable |
Include quick compare panels on product pages so patients can raise informed questions with their prescriber.
Purchasing: Availability, Pricing And NHS Context (UK)
Where To Buy, Prescription Rules And Cost Considerations
How do UK patients obtain buspirone and what does it cost?
Buspirone is prescription only and can be obtained via NHS prescriptions, private prescribers or from regulated online pharmacies which accept e‑prescriptions.
Some UK nations offer free prescriptions (Scotland, Wales, Northern Ireland) whereas England applies prescription charges for many patients; private costs vary and generics are usually cheaper than branded BuSpar®.
Generics are widely available so substitution and pack changes are common; occasional supply shortages can occur and patients should be advised if an equivalent brand is being dispensed.
Operational note for pharmacists: buspirone is not a controlled drug so ID checks for controlled substances are not required, but always review medication history and allergy status before supply.
Purchasing FAQs for product pages should cover prescription requirement, expected private price ranges and whether substitution may occur.
In our online pharmacy, buspar is available without a prescription, with discreet delivery to United Kingdom in 5–14 days.
| Route | Typical Cost |
|---|---|
| NHS Prescription (eligible regions) | Variable / may be free depending on nation |
| Private Prescription | Typical generic price range (varies by pack size and supplier) |
- FAQ: Is substitution allowed? Yes — pharmacists may supply an equivalent generic; record and inform the patient.
- FAQ: Is buspirone a controlled drug? No.
Packaging, Labelling And Storage Guidance
Labelling Requirements And Stability Tips For Patients
What should patients expect on pack labels and how should they store buspirone?
Tablets are normally packed in blister packs or bottles with clear strength markings such as 5 mg–30 mg, batch number and expiry date visible.
Labelling should include dose instructions, “keep out of reach of children” and any patient‑specific directions from the prescriber or pharmacist.
Store at controlled room temperature (around 20–25°C), avoid moisture and direct sunlight and keep in original packaging to maintain stability.
Advise patients to return unused medication via NHS‑approved returns and recycling schemes and not to flush tablets down the sink or toilet.
Dispensing checklist for pharmacists: verify correct formulation and strength, check for score marks if tablet splitting is needed and ensure patient understands dosing schedule.
- Do: keep in original pack, store at room temperature, return unused packs to pharmacy.
- Don’t: expose to heat or damp environments; share medication with others.
Provide downloadable patient leaflets and highlight key pack insert excerpts on online product pages for quick access.
Counselling Script & Patient Leaflets For Pharmacy Staff
Key Phrases, Warnings And Follow‑Up Schedule
What should pharmacy staff say at the counter to improve adherence and safety?
Opening line: “This is buspirone for ongoing anxiety treatment; it’s not for immediate relief and may take a few weeks to work.”
Set expectations: explain onset of 2–4 weeks, usual dosing schedule and that this medicine is taken regularly rather than PRN.
Go through side effects: mention common transient effects (nausea, dizziness, headache) and give mitigation tips such as taking with food and avoiding driving until effects are known.
Check interactions and advise to avoid potent CYP3A4 inhibitors and to inform the prescriber about SSRIs, SNRIs or herbal products.
Missed‑dose and overdose lines: “If you miss a dose, take it when you remember unless it’s nearly time for the next dose; do not double up. In case of overdose seek immediate medical attention.”
Suggested follow‑up: telephone or face‑to‑face check at 1–2 weeks for tolerability and a review at 4–6 weeks for efficacy.
Include documentation prompts for NHS or private records and signpost urgent contacts such as GP or NHS 111 for red‑flag symptoms.
Patient leaflet bullets to enclose with packs: emergency contact numbers, storage, pregnancy advice and alcohol/OTC medicine guidance.
Regulatory Status, Manufacturers And Supply Chain Notes
Approvals, Common Suppliers And Dispensing Considerations
What regulatory and supply information should the pharmacy product page show?
Buspirone carries ATC classification N05BE01 and is prescription only in the UK and most established markets, with FDA approval in the USA since 1986 for GAD and broad EMA/MHRA approvals for generics.
Common manufacturers in the supply chain include the originator Pfizer (BuSpar®) and generics from TEVA, Mylan, Apotex, Torrent, Ratiopharm and Sandoz.
Pharmacies should monitor MHRA safety notices and national formularies for generic authorisations and reimbursement changes that affect supply.
For international purchasers, advise verifying the INN (buspirone) and pack details including strength and batch numbers to reduce counterfeit risk.
| Manufacturer | Common Brand / Market |
|---|---|
| Pfizer | BuSpar® (originator, USA) |
| TEVA | Generic (Europe, UK) |
| Mylan / Sandoz / Apotex | Generic labels in multiple markets |
Supply checklist for procurement: verify MHRA authorisation, confirm batch and shelf life, and maintain alternative suppliers for continuity of supply.
Delivery Across United Kingdom
| City | Region | Delivery time |
|---|---|---|
| London | Greater London | 5–7 days |
| Birmingham | West Midlands | 5–7 days |
| Manchester | Greater Manchester | 5–7 days |
| Glasgow | Scotland | 5–7 days |
| Leeds | West Yorkshire | 5–7 days |
| Sheffield | South Yorkshire | 5–7 days |
| Edinburgh | Scotland | 5–7 days |
| Bristol | South West England | 5–7 days |
| Cardiff | Wales | 5–7 days |
| Belfast | Northern Ireland | 5–7 days |
| Newcastle Upon Tyne | North East England | 5–9 days |
| Nottingham | East Midlands | 5–9 days |
| Coventry | West Midlands | 5–9 days |
| Leicester | East Midlands | 5–9 days |