Novonorm
In brief
- In our pharmacy, you can buy Novonorm without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Novonorm (repaglinide) is used to treat type 2 diabetes mellitus as an adjunct to diet and exercise; it is a rapid‑acting meglitinide that stimulates pancreatic beta cells to release insulin by closing ATP‑dependent potassium channels, reducing post‑prandial glucose spikes.
- The usual starting dose for adults is 0.5 mg orally with each main meal, taken 0–30 minutes before the meal; the dose may be titrated at weekly intervals up to a maximum single dose of 4 mg and a total daily maximum of 16 mg.
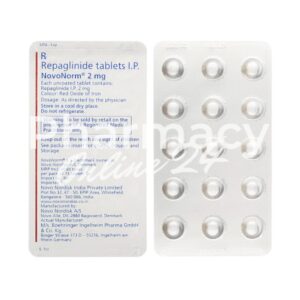
- The form of administration is oral tablets (available in 0.5 mg, 1 mg and 2 mg strengths), taken just before meals (0–30 minutes prior).
- Onset of effect is rapid, typically within about 15–30 minutes.
- Duration of action is short, generally around 4–6 hours, targeting mealtime glucose excursions.
- Do not consume excessive alcohol; alcohol can increase the risk of hypoglycaemia and mask symptoms, so avoid alcohol and monitor blood sugar closely.
- The most common side effect is hypoglycaemia; other common adverse effects include headache, upper respiratory tract infections and gastrointestinal upset.
- Would you like to try Novonorm without a prescription?
Legal status and availability in the UK
Novonorm is a prescription-only medicine (POM) in the UK.
In our online pharmacy, Novonorm is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Basic Novonorm information
- INN (international nonproprietary name): Repaglinide
- Brand names available in the United Kingdom: NovoNorm
- ATC code: A10BX02
- Forms and dosages: Tablets 0.5 mg, 1 mg, 2 mg
- OTC / Rx classification: Prescription-only medicine (POM)
What NovoNorm (repaglinide) is: active ingredient and formulations
INN, ATC code and drug class
Repaglinide is the International Nonproprietary Name for this medicine.
The ATC code is A10BX02, classifying it as an oral blood glucose-lowering drug in the meglitinide (glinide) group.
It is a rapid-acting insulin secretagogue intended for lowering post-prandial glucose in type 2 diabetes.
Manufacturer and pack forms
NovoNorm is made by Novo Nordisk, and generic repaglinide is also available.
Tablets are marketed in strengths of 0.5 mg, 1 mg and 2 mg.
Indications and practical patient selection
Who benefits most in routine care
Repaglinide is licensed for adults with type 2 diabetes as an adjunct to diet and exercise to control post-prandial glucose excursions.
It is particularly useful where mealtime spikes are the main problem.
Patients with irregular eating patterns, such as shift workers, often find a mealtime agent convenient.
It is also an option where metformin is unsuitable or not tolerated due to gastrointestinal side effects.
When not to choose repaglinide
Repaglinide must not be used in type 1 diabetes or diabetic ketoacidosis; these are absolute contraindications.
Do not choose repaglinide when long-acting basal control is the main target and a weight-neutral therapy is preferred.
Alternatives include metformin as first-line, or SGLT2 and DPP‑4 inhibitors for different risk profiles.
In patients with severe hepatic impairment repaglinide is contraindicated and alternatives should be selected.
Dosage, timing and titration
Standard adult dosing strategy
The usual starting dose is 0.5 mg orally with each main meal.
Administer each dose 0–30 minutes before the meal so the secretagogue effect aligns with food intake.
If a meal is skipped, skip that dose and do not double the next dose.
Titration steps and maximum doses
Increase the dose at weekly intervals based on blood-glucose monitoring and tolerability.
Common titration increments follow 0.5 mg → 1 mg → 2 mg steps per meal as clinically indicated.
The maximum single dose is 4 mg and the maximum total daily dose is 16 mg.
| Dose step | When to use | Monitoring |
|---|---|---|
| 0.5 mg with each main meal | Usual initial dose | Daily pre- and post-prandial glucose checks for the first week |
| 1 mg with each main meal | After up-titration | Daily glucose logs; review at 1 week |
| 2 mg with each main meal | Second titration step if control insufficient | Frequent self-monitoring; consider GP review |
| Up to 4 mg per meal (max 16 mg/day) | Only if required and tolerated | Clinical review and HbA1c monitoring |
Blood-glucose monitoring is used during titration, with follow-up within 1–4 weeks of a dose change. If hypoglycaemia occurs, the dose is reduced and meal timing or the choice of therapy is reassessed.
Contraindications and warnings
Absolute contraindications and high-risk scenarios
Absolute contraindications include type 1 diabetes mellitus and diabetic ketoacidosis.
Hypersensitivity to repaglinide or any excipients is an absolute contraindication.
Concomitant use of gemfibrozil is contraindicated because of the risk of severe hypoglycaemia.
Severe hepatic impairment is also a contraindication for repaglinide use.
- Gemfibrozil interaction: contraindicated — avoid co-prescribing.
- Hepatic impairment: severe disease contraindicates use; mild–moderate requires caution.
- Elderly: increased hypoglycaemia risk — start low and monitor.
Side effects, hypoglycaemia management and patient counselling
Common adverse effects
The most clinically important adverse effect is hypoglycaemia.
Other common reactions include headache, upper respiratory tract infections, back pain and gastrointestinal upset.
Advise patients to recognise symptoms such as sweating, tremor and confusion and to carry fast-acting carbohydrate at all times.
Tell patients to check their blood glucose if they feel unwell or suspect low sugar.
Warn about alcohol because it can increase risk of hypoglycaemia with insulin secretagogues.
Emergency actions for hypoglycaemia
For mild hypoglycaemia, advise oral glucose or a sugary drink and retest blood glucose after 10–15 minutes.
If symptoms persist or worsen, give another 15–20 g of fast-acting carbohydrate and seek urgent medical help.
In severe hypoglycaemia where the patient is unconscious, emergency services and intravenous glucose or intramuscular glucagon are required.
Drivers should check blood glucose before driving when in doubt, and record any hypoglycaemic episodes.
- Step 1: Stop activity and check blood glucose immediately.
- Step 2: Take 15–20 g fast-acting carbohydrate (glucose gel, dextrose, sugary drink).
- Step 3: Recheck after 10–15 minutes and repeat if necessary, then eat a small snack or meal if next meal is not imminent.
Drug interactions — clinically relevant pairs and management
High-risk interactions (gemfibrozil, strong CYP inhibitors)
The key interaction to flag is gemfibrozil, which is contraindicated due to severe hypoglycaemia risk.
Repaglinide is metabolised via CYP enzymes and exposure can be increased by strong CYP3A4 and CYP2C8 inhibitors.
Strong inhibitors such as certain azole antifungals, macrolides and protease inhibitors can increase repaglinide levels and hypoglycaemia risk.
Enzyme inducers may reduce repaglinide exposure and reduce glycaemic effect.
If an interacting medicine cannot be avoided, the prescriber may reduce the dose, intensify glucose monitoring or choose an alternative therapy.
| Drug | Effect on repaglinide | Action |
|---|---|---|
| Gemfibrozil | Marked increase in repaglinide exposure; severe hypoglycaemia risk | Contraindicated — do not take together; tell the prescriber |
| Ketoconazole (azole antifungals) | May increase repaglinide levels | Consider dose reduction; monitor glucose closely |
| Clarithromycin (macrolide) | May increase repaglinide exposure | Closer monitoring; discuss with the prescriber |
| Rifampicin (inducer) | May reduce repaglinide levels | Monitor for loss of efficacy; discuss alternative |
Special populations — elderly, renal/hepatic impairment, pregnancy, paediatrics
Guidance for elderly and comorbid patients
Elderly patients are at higher risk of hypoglycaemia and should start on the lowest available dose.
Renal impairment requires cautious titration from 0.5 mg with close glucose monitoring.
Severe hepatic impairment is a contraindication; in mild to moderate disease start low and monitor liver function and glucose control.
Pregnancy, breastfeeding and children
Safety and efficacy in children have not been established and repaglinide is generally not recommended in paediatrics.
Pregnancy and breastfeeding cases should be managed by specialist teams, and insulin remains the preferred treatment when tight control is required in pregnancy.
Advise pregnant or breastfeeding patients to discuss therapy with their GP or diabetes clinic before continuing or starting repaglinide.
| Condition | Recommended action |
|---|---|
| Elderly | Start low, monitor frequently, consider alternatives if recurrent hypoglycaemia |
| Renal impairment | Start at 0.5 mg, titrate cautiously with frequent glucose checks |
| Severe hepatic impairment | Contraindicated |
| Pregnancy/Breastfeeding | Specialist management; insulin preferred in many cases |
| Paediatrics | Not established — generally not recommended |
Comparing repaglinide with alternatives
When to prefer meglitinides over sulfonylureas/metformin
Repaglinide and sulfonylureas are both secretagogues, but repaglinide is shorter acting and better suited for mealtime control.
That shorter action often results in a lower risk of prolonged hypoglycaemia compared with some sulfonylureas.
Repaglinide is not first-line versus metformin; choose it when metformin is contraindicated or not tolerated.
Combination therapy such as repaglinide plus metformin can target fasting and post-prandial glucose together.
Monitoring burden and combination strategies
Mealtime agents require good awareness of meal timing and self-monitoring.
| Drug class | Pros | Cons |
|---|---|---|
| Meglitinides (repaglinide) | Rapid-acting for mealtime spikes; flexible dosing | Hypoglycaemia risk; multiple daily dosing |
| Sulfonylureas | Effective | Longer action; higher risk of prolonged hypoglycaemia |
| Metformin | First-line; weight-neutral; low hypoglycaemia risk | Gastrointestinal side effects; contraindicated in some renal disease |
| DPP-4 / SGLT2 / GLP-1 | Lower hypoglycaemia risk; additional benefits depending on class | Class-specific adverse effects |
Storage
Store repaglinide at 25°C with permitted excursions between 15–30°C and protect from moisture and heat.
Keep tablets in the original packaging until use to protect stability and to retain the patient leaflet.
Avoid storing tablets in bathrooms or near heat sources.
Practical counselling points
What patients should know
Explain timing carefully: take the tablet 0–30 minutes before the main meal for best effect.
Tell patients to skip the dose for any meal they do not eat and not to double up at the next meal.
Describe hypoglycaemia symptoms and the immediate treatment steps and encourage carrying fast-acting carbohydrate.
Advise patients to avoid or be cautious with alcohol because of increased hypoglycaemia risk.
Remind patients to inform their prescriber about all medicines, including over-the-counter products and herbal supplements.
Delivery across the United Kingdom
| City | Region | Delivery time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Manchester | England | 9–21 days |
| Leeds | England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Bristol | England | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Newcastle Upon Tyne | England | 9–21 days |
| Southampton | England | 9–21 days |
| Nottingham | England | 9–21 days |
| Aberdeen | Scotland | 9–21 days |
| Brighton | England | 9–21 days |