Revia
In brief
- In our pharmacy, you can buy Revia without a prescription, with delivery across the United Kingdom in 9–21 days; discreet and anonymous packaging is available.
- Revia (naltrexone hydrochloride) is used to prevent relapse in opioid dependence and to reduce craving in alcohol use disorder; it is an opioid receptor antagonist that blocks μ‑opioid receptors.
- The usual adult dose is 50 mg orally once daily.
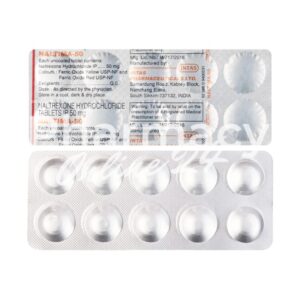
- The form of administration is oral film‑coated 50 mg tablets (blister packs or bottles).
- The effect begins for oral naltrexone within about 30–60 minutes (peak levels ≈1 hour).
- The duration of action for oral naltrexone is approximately 24 hours (daily dosing).
- Alcohol warning: avoid excessive alcohol consumption and use with caution if there is hepatic impairment—do not use in acute hepatitis or liver failure and monitor liver function regularly.
- The most common side effect is nausea; other frequent effects include headache, insomnia, anxiety, tiredness, joint or muscle pain and loss of appetite.
- Would you like to try Revia without a prescription?
Basic Revia information
- INN (international nonproprietary name): Naltrexone hydrochloride
- Brand names available in the United Kingdom: Revia (brand discontinued; generic naltrexone 50 mg tablets are available)
- ATC code: N07BB04
- Forms and dosages: 50 mg oral tablets (film‑coated, scored)
- Manufacturers in the United Kingdom: generic naltrexone tablets from manufacturers such as Teva, Sandoz and Accord Healthcare
- Registration status in the United Kingdom: Prescription-only medicine (POM)
- OTC / Rx classification: Prescription-only medicine (POM)
Legal status and availability in the UK
Naltrexone (Revia) is a prescription-only medicine (POM) in the UK.
In our online pharmacy, Revia is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Indications and place in therapy
Licensed indications
Which conditions is naltrexone licensed for?
Naltrexone hydrochloride is licensed in the UK for relapse prevention in opioid dependence; it is also used under specialist guidance in alcohol dependence.
Role in treatment pathways
Where does naltrexone fit compared with other treatments?
Naltrexone is an opioid antagonist used for relapse prevention rather than management of opioid withdrawal.
It forms part of medication‑assisted treatment (MAT) where the goal is to reduce relapse risk and support recovery, but it is most effective when combined with psychosocial and relapse‑prevention programmes.
Important practical point for opioid users: initiation requires an opioid‑free window of 7–10 days to avoid precipitated withdrawal.
| Formulation | Indication |
|---|---|
| 50 mg oral tablet | Opioid relapse prevention (when opioid‑free); alcohol dependence under specialist guidance |
Dosage regimens and practical administration tips
Standard dosing by indication
What dose should most adults expect?
The usual oral dose for adults is 50 mg once daily.
Tablets are film‑coated and scored.
Missed dose and storage reminders
| Scenario | Advice |
|---|---|
| Missed oral dose | Take as soon as remembered unless close to the next dose. Do not double up. |
| Storage | Store tablets at 20–25°C. |
- Do: follow the written dosing instructions; tablets may be taken with or without food.
- Don’t: start naltrexone without completing a 7–10 day opioid‑free period.
Contraindications, warnings and baseline checks
Absolute contraindications
Who must not start naltrexone?
- Patients currently using opioids or in acute opioid withdrawal — initiation can precipitate severe withdrawal.
- Those with acute hepatitis or significant hepatic impairment.
- Known hypersensitivity to naltrexone or any excipient in the formulation.
Baseline investigations and safety checks
Which baseline tests are required?
- Obtain baseline liver function tests (LFTs) prior to initiation.
- Confirm opioid‑free status for 7–10 days in those with recent opioid exposure.
- Document pregnancy status and counsel women of childbearing potential; discuss breastfeeding risks.
Definitions:
- Acute hepatitis: recent onset liver inflammation with elevated transaminases — do not start naltrexone.
- Chronic liver disease: long‑standing hepatic impairment — use with caution and close monitoring.
Side effects, adverse events and how to monitor
Common adverse effects
What side effects should patients expect?
- Nausea and headache are common and typically transient.
- Insomnia, joint or muscle pain, anxiety, tiredness and loss of appetite are also reported.
- Most side effects are dose‑dependent and often subside with ongoing therapy.
Serious risks and when to act
What are the red flags?
| Common | Serious |
|---|---|
| Nausea, headache, insomnia, mild anxiety | Hepatotoxicity (marked transaminase rise), severe abdominal pain, jaundice |
- Red flags: seek immediate review for jaundice, dark urine, severe abdominal pain or unexplained tiredness.
- Mental health monitoring: screen for depression and suicidal ideation and arrange prompt follow‑up if mood changes occur.
- In suspected overdose, emergency care is required because severe hepatotoxicity is possible.
Report suspected side effects through the MHRA Yellow Card scheme.
Drug interactions and switching from opioids
Key interactions
How does naltrexone interact with opioids and other medicines?
- Naltrexone blocks opioid receptors and will reverse or blunt opioid analgesia.
- Concurrent opioid analgesics will be functionally antagonised, reducing pain control.
- Be mindful of other hepatically metabolised medications when polypharmacy exists; monitor liver function as needed.
Safe switching strategies
How to switch a patient from agonist therapy to naltrexone?
For opioid‑dependent patients, ensure a 7–10 day opioid‑free interval before initiating oral naltrexone to avoid precipitated withdrawal.
Document naltrexone on emergency care notes and advise patients that acute opioid analgesia will require specialist advice while taking naltrexone.
Special populations — elderly, pregnancy, adolescents
Age and paediatric considerations
Can children or adolescents use naltrexone?
Safety and effectiveness in those under 18 are not established and use is not recommended for children and adolescents.
Elderly patients may be treated with naltrexone with caution; monitor renal and hepatic function and individualise therapy.
Pregnancy, breastfeeding and frailty
What about pregnancy and breastfeeding?
- Pregnancy: weigh risks and benefits and document shared decision‑making.
- Breastfeeding: discuss potential risks and consider specialist input before starting naltrexone.
- Hepatic or renal impairment: avoid in acute hepatitis or liver failure; use caution with closer LFT monitoring in moderate impairment.
Definition list (use):
- Use not recommended: scenarios where evidence is absent or risk is significant (children under 18, acute hepatitis).
- Use with caution: elderly, moderate hepatic/renal impairment, pregnancy after documented counselling.
Counselling points
Essential counselling points
What should patients be told about naltrexone?
- Explain purpose: relapse prevention for alcohol dependence or opioid relapse prevention.
- Emphasise: do not use opioids while on naltrexone; confirm opioid‑free period when relevant.
- Review common side effects, advise when to stop and seek review (jaundice, severe abdominal pain, mood changes).
- Discuss missed dose advice.
- Advise on liver monitoring and the need for baseline and periodic LFTs.
Safety nets and follow-up
- Refer to local addiction services and psychosocial support — medication alone is rarely sufficient.
- Provide emergency advice: if urgent opioid analgesia is needed or signs of hepatic injury occur, seek urgent care.
Packaging and storage
- Tablets: 50 mg film‑coated, scored tablets in blisters or bottles.
- Store tablets at 20–25°C; protect from moisture and excess heat.
Alternatives and switching considerations
Pharmacologic alternatives
What other medicines are used for alcohol or opioid dependence?
| Drug | Indication | Mechanism |
|---|---|---|
| Disulfiram | Alcohol dependence | Alcohol aversive agent |
| Acamprosate | Alcohol dependence | Modulates glutamate/GABA |
| Methadone | Opioid dependence | Full opioid agonist |
| Buprenorphine | Opioid dependence | Partial opioid agonist/antagonist |
| Nalmefene | Alcohol dependence | Opioid receptor antagonist |
When to choose naltrexone vs others
Which patients are best suited to naltrexone?
- Naltrexone suits motivated patients who can remain opioid‑free and who will engage with psychosocial support.
- Methadone or buprenorphine remain first‑line for active opioid dependence because of agonist effects that support stabilisation.
Delivery across the United Kingdom
| City | Region | Delivery time |
|---|---|---|
| London | Greater London | 9–21 days |
| Birmingham | West Midlands | 9–21 days |
| Manchester | Greater Manchester | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Leeds | West Yorkshire | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Bristol | South West England | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Sheffield | South Yorkshire | 9–21 days |
| Newcastle | Tyne and Wear | 9–21 days |
| Nottingham | Nottinghamshire | 9–21 days |
| Southampton | Hampshire | 9–21 days |
| Plymouth | Devon | 9–21 days |