Avelox
In brief
- In our pharmacy, you can buy Avelox without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Avelox (moxifloxacin) is used to treat bacterial infections such as community-acquired pneumonia, acute bacterial sinusitis, acute bacterial exacerbations of chronic bronchitis, complicated skin and intra‑abdominal infections, and pelvic inflammatory disease; it is a fluoroquinolone that inhibits bacterial DNA gyrase (topoisomerase II) and topoisomerase IV, preventing DNA replication and cell division.
- The usual dose is 400 mg once daily for adults, with duration depending on the indication (for example 5 days for exacerbation of chronic bronchitis, 7–14 days for pneumonia, 7–10 days for sinusitis, 14 days for pelvic inflammatory disease and 7–21 days for complicated skin infections or as directed by a clinician).
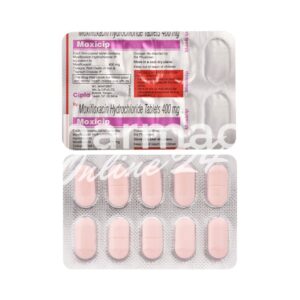
- The form of administration is oral film-coated tablet (400 mg) or intravenous infusion (400 mg in 250 mL flexibag) for hospital use.
- Plasma concentrations peak within about 1–3 hours after an oral dose; clinical improvement is often seen within 48–72 hours depending on the infection and patient factors.
- Duration of action: the elimination half-life is approximately 12 hours, allowing once‑daily dosing with antibacterial effects that persist for about 24 hours per dose.
- Do not consume alcohol while taking Avelox, as alcohol can worsen side effects such as dizziness and impair recovery.
- The most common side effect is nausea.
- Would you like to try Avelox without a prescription?
Legal status and availability in the UK
Avelox (moxifloxacin) is a prescription-only medicine (POM) in the UK.
In our online pharmacy, Avelox is available without a prescription, with discreet delivery to the United Kingdom in 5‑14 days.
Basic Avelox information
- INN (international nonproprietary name): Moxifloxacin
- Brand names available in the United Kingdom: Avelox (400 mg film-coated tablets)
- ATC code: J01MA14
- Forms & Dosages: Film-coated tablet 400 mg (oral); IV solution/flexibag 400 mg/250 mL (0.8% NaCl) for infusion
- Manufacturers in the United Kingdom: Bayer
- Registration status in the United Kingdom: Licensed by the MHRA
- OTC / Rx classification: Prescription-only medicine (POM)
Product overview: what Avelox (moxifloxacin) is
Active ingredient, classification and origin
What is in an Avelox tablet?
Avelox contains the active ingredient moxifloxacin, an 8‑methoxy fluoroquinolone with ATC code J01MA14.
Avelox is made by Bayer.
Avelox is available as 400 mg film‑coated tablets for oral use and as 400 mg/250 mL IV flexibags for infusion.
It is licensed as a systemic antibacterial with activity against many respiratory pathogens and selected skin and intra‑abdominal organisms.
Indications and typical dosage regimens
NHS‑relevant indications and practical dosing
Which infections is Avelox licensed for and how is it usually dosed?
Avelox is licensed for community‑acquired pneumonia, acute bacterial sinusitis, acute bacterial exacerbation of chronic bronchitis, complicated skin and soft tissue infections (often with IV to oral switch), complicated intra‑abdominal infections and pelvic inflammatory disease.
Adult dosing is standardised to 400 mg once daily for most indications.
Course length depends on the infection and clinical response.
| Indication | Dose | Typical duration |
|---|---|---|
| Community‑acquired pneumonia | 400 mg once daily | 7–14 days |
| Acute bacterial sinusitis | 400 mg once daily | 7–10 days |
| Exacerbation of chronic bronchitis | 400 mg once daily | 5 days |
| Complicated skin/soft‑tissue | 400 mg once daily | 7–21 days |
| Complicated intra‑abdominal | 400 mg once daily | 5–14 days |
| Pelvic inflammatory disease | 400 mg once daily | 14 days |
Prescribers should follow local antimicrobial guidelines and culture results when choosing Avelox.
Formulations, packaging and hospital use
Tablet and IV presentations; pack sizes and routes
Oral Avelox is supplied as 400 mg film‑coated tablets commonly in blisters of 5, 7 or 10 tablets per box.
The IV presentation is supplied as a 400 mg/250 mL flexibag in 0.8% sodium chloride for single infusion use in hospital settings.
IV Avelox is reserved for severe infections or when oral therapy is not possible, with an early IV→oral switch once the patient can tolerate oral intake.
| Formulation | Strength | Packaging | Route |
|---|---|---|---|
| Film‑coated tablet | 400 mg | Blisters (5/7/10) | Oral |
| IV solution (flexibag) | 400 mg/250 mL (0.8% NaCl) | Single‑use flexibag | Intravenous infusion |
Contraindications and cautions
Absolute contraindications and high‑risk scenarios
Who must not take Avelox?
Absolute contraindications include known hypersensitivity to moxifloxacin or other quinolones, previous quinolone‑associated tendon disorders, and a history of myasthenia gravis due to risk of exacerbation.
Relative contraindications where caution is required include known prolonged QT interval, concurrent use of QT‑prolonging drugs, uncorrected hypokalaemia, severe bradycardia and heart failure.
Concomitant systemic corticosteroids raise the risk of tendon rupture and warrant careful review.
- Contraindication: Hypersensitivity — do not supply and notify prescriber.
- Contraindication: Tendon disorder history — avoid and recommend alternative.
- Caution: QT risk — consider ECG and drug interaction review.
Pharmacists should flag interactions and escalate to prescribers and recommend ECG monitoring where indicated.
Side effects: common to severe and monitoring
What to warn patients about and when to act
What symptoms should patients report immediately while taking Avelox?
Warn patients about common adverse effects such as nausea, diarrhoea, headache, dizziness and mild rash.
Highlight serious risks that require immediate action: acute tendon pain or swelling, new numbness or tingling suggesting peripheral neuropathy, severe CNS effects like confusion or hallucinations, signs of liver injury such as jaundice, and cardiac symptoms including syncope or palpitations.
Regulatory warnings emphasise tendonitis, tendon rupture, peripheral neuropathy and central nervous system effects.
- Red flag: Sudden tendon pain — stop medication and seek urgent medical review.
- Red flag: New peripheral numbness — discontinue and report.
- Red flag: Jaundice or severe abdominal pain — arrange liver function assessment.
Suspected adverse reactions should be reported via the MHRA Yellow Card scheme.
Drug interactions and cardiac safety (QT)
Key interacting medicines and management
Which medicines increase cardiac or tendon risk when given with Avelox?
Moxifloxacin can prolong the QT interval and should be avoided with other QT‑prolonging medicines such as class IA and class III antiarrhythmics, some antidepressants, macrolides and certain antipsychotics.
Drugs or conditions that lower electrolytes, notably hypokalaemia, raise torsade risk and should be corrected before and during therapy.
Concomitant systemic corticosteroids increase tendon rupture risk and require caution.
Also counsel on multivalent cations such as antacids, iron, zinc and sucralfate; although interaction is less pronounced than with some quinolones, advise spacing doses.
| Interacting drug class | Effect | Pharmacy action |
|---|---|---|
| Antiarrhythmics (Class IA/III) | Increased QT prolongation | Avoid co‑administration; consult prescriber; ECG if necessary |
| Macrolide antibiotics | Increased QT and additive toxicity | Do not combine; choose alternative based on sensitivity |
| Systemic corticosteroids | Higher tendon rupture risk | Review risk/benefit and monitor tendons closely |
| Antacids / Iron / Zinc | Reduced oral absorption if co‑administered | Space doses by at least 2–4 hours |
Recommend ECG monitoring in high‑risk patients and follow an escalation pathway to the prescriber for any concerns.
Use in special populations
Practical guidance and dosing adjustments
Can patients with kidney, liver or pregnancy concerns take Avelox?
Children and adolescents under 18 are not recommended to use Avelox due to musculoskeletal adverse effect risk.
Elderly patients do not require routine dose adjustment but need closer monitoring for QT prolongation and tendon events, taking comorbidities into account.
No dose adjustment is required in renal impairment or hepatic impairment, but monitor for adverse effects and review fluid balance when using IV fluids in renal failure.
Pregnancy and breastfeeding should prompt careful discussion; Avelox is generally avoided unless the potential benefit outweighs the risk and alternatives have been considered.
- Children: Contraindicated — counsel and suggest alternatives.
- Elderly: Monitor for tendon and cardiac warnings; review concomitant drugs.
- Renal/hepatic: No routine dose change but observe clinically.
Administration, missed dose and overdose instructions
How to take, storage and emergency actions
What practical instructions should patients receive for safe use at home?
Tablets should be taken whole with a full glass of water and may be taken with or without food.
If a dose is missed, take it as soon as remembered unless the next dose is due; do not double up on doses.
In overdose, seek emergency medical attention promptly; supportive care and ECG monitoring for QT prolongation are priorities.
Store tablets at 20–25°C, keeping them dry and protected from light; transport is allowed at 15–30°C.
IV bags should be stored according to hospital protocols and must not be frozen.
- Patient steps: Take once daily at the same time each day and finish the course.
- Emergency: For suspected overdose, call emergency services and mention moxifloxacin and any co‑medications.
IV to oral switch and hospital pharmacy considerations
When to use IV, switching criteria and discharge packs
When is it safe to move a patient from IV Avelox to oral tablets?
IV Avelox is for hospitalised patients who cannot tolerate oral therapy or have severe infections requiring parenteral therapy.
Switch criteria include improving clinical signs, ability to take and absorb oral medication, stable haemodynamics and afebrile status.
An early IV→oral switch reduces length of stay and IV‑line complications and is part of good antimicrobial stewardship.
| IV indications | Monitoring | Switch criteria |
|---|---|---|
| Severe infection or inability to tolerate oral intake | Renal/liver function, ECG if QT risk, infusion site care | Improving signs, tolerating oral fluids/food, stable vitals |
Alternatives and when to prefer Avelox
Comparison with other antibiotics
How does Avelox compare with other fluoroquinolones and when is it preferred?
Alternatives include levofloxacin, ciprofloxacin and ofloxacin, plus other antibiotic classes chosen on culture and sensitivity results.
Avelox offers enhanced activity against atypical respiratory pathogens and some gram‑positive organisms, which can make it attractive for certain respiratory infections.
However, its safety profile and stewardship considerations often reserve it as a second‑line option for uncomplicated sinusitis or bronchitis.
| Drug | Typical indications | Pros / cons |
|---|---|---|
| Moxifloxacin (Avelox) | Respiratory, intra‑abdominal, skin | Good atypical coverage; QT and tendon risk |
| Levofloxacin | Respiratory, urinary | Broad activity; different safety profile and resistance patterns |
| Ciprofloxacin | Urinary, some systemic infections | Less reliable for some respiratory pathogens |
Choose based on microbiology, local susceptibility patterns and individual patient comorbidities, and involve microbiology or infectious disease specialists for severe cases.
FAQs
- Can I take Avelox with an antacid? — Advise spacing doses by 2–4 hours.
- Is it safe in pregnancy? — Generally avoid unless benefit outweighs risk; counsel and document.
- What if I miss a dose? — Take as soon as remembered unless near next dose; do not double up.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Liverpool | England | 9–21 days |
| Leeds | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Bristol | England | 9–21 days |
| Newcastle Upon Tyne | England | 9–21 days |
| Nottingham | England | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Coventry | England | 9–21 days |
| Leicester | England | 9–21 days |
Final notes
Report suspected adverse reactions via the Yellow Card scheme and seek urgent review for red‑flag symptoms.