Exocin
In brief
- Exocin (ofloxacin 0.3% eye drops) is generally prescription-only in the UK and most regulated markets, but it can sometimes be obtained directly from some pharmacies without a prescription depending on local pharmacy policy; check with your local pharmacist for availability and legal requirements.
- Exocin is used to treat bacterial eye infections such as bacterial conjunctivitis and corneal ulcer; it is a fluoroquinolone ophthalmic anti-infective that works by inhibiting bacterial DNA gyrase and topoisomerase IV, preventing bacterial DNA replication and causing bacterial cell death.
- Usual dosing for adults: for bacterial conjunctivitis, 1–2 drops into the affected eye(s) every 2–4 hours for the first 2 days then every 4–6 hours up to 7 days; for corneal ulcer, 1–2 drops every 30–60 minutes on day 1, then hourly and later reduced to every 4 hours, treatment often continuing up to 14 days; paediatric dosing generally same from 1 year upwards.
- Form of administration: ophthalmic solution (eye drops), typically 0.3% (3 mg/mL) in multi‑dose LDPE bottles or single‑dose units; available as preservative‑free or with benzalkonium chloride in some presentations.
- Onset time: antibacterial activity begins soon after instillation and clinical improvement is often seen within 24–48 hours, though full resolution may take longer depending on infection severity.
- Duration of action: a single dose provides local activity for approximately 4–6 hours (hence dosing intervals); typical treatment courses are about 7 days for conjunctivitis and up to 14 days for corneal ulcers, guided by clinical response.
- Alcohol warning: there is no known significant interaction between topical ofloxacin eye drops and alcohol; drinking alcohol is unlikely to affect the eye drops’ local effectiveness, though excessive alcohol intake is best avoided for general health and if you are advised otherwise by a clinician.
- The most common side effect is local eye irritation — stinging, burning, redness or mild discomfort after instillation; blurred vision and eye dryness may also occur.
- Would you like to try exocin without a prescription?
Basic Exocin Information
- INN (International Nonproprietary Name): Ofloxacin (Ofloxacin in some languages and regulatory texts)
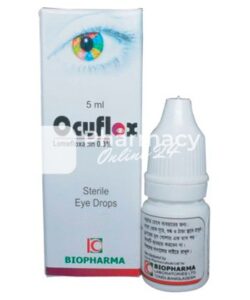
- Brand Names Available In United Kingdom: Ocuflox, Exocin
- ATC Code: S01AE01 — S01 = Ophthalmologicals; AE = Fluoroquinolones; 01 = Ofloxacin
- Forms & Dosages: Typically 0.3% (3 mg/mL) ophthalmic solution supplied in 5 mL LDPE multi‑dose bottles; preservative‑free single‑dose units are co‑marketed in some settings; preserved versions may contain benzalkonium chloride
- Manufacturers In United Kingdom: Major global suppliers include Allergan (AbbVie), Santen Pharmaceutical, Dr. Reddy’s and Alcon; local generic suppliers may also market ofloxacin formulations
- Registration Status In United Kingdom: Rx‑only with national registrations; regulatory oversight by MHRA and national product literature applies
- OTC / Rx Classification: Prescription Only (Rx‑only) in the UK and most other markets
Market Realities & Patient Experiences
Availability In UK Pharmacies And Online
Ofloxacin ophthalmic 0.3% is sold widely under regional brands such as Ocuflox and Exocin in many European markets and the UK.
The standard strength is 3 mg/mL and common pack sizes are 5 mL multi‑dose bottles.
In the United Kingdom the product is classified Rx‑only and needs a valid prescription to be supplied in the usual clinical pathway.
High‑street chains such as Boots, LloydsPharmacy and Superdrug routinely dispense ophthalmic antibiotics against an NHS or private prescription, and online pharmacies provide validated prescription services for home delivery.
Electronic prescriptions are now common in NHS care and speed up collection from community pharmacies.
Patients report fast symptomatic relief from bacterial conjunctivitis with ofloxacin eye drops but commonly mention short‑lived stinging on instillation and brief blurred vision afterwards.
Regional differences in cost matter: Scotland, Wales and Northern Ireland have prescription exemptions that often remove out‑of‑pocket charges, whereas patients in England usually pay the standard NHS prescription charge unless exempt.
Typical Patient Journeys & Complaints
A typical patient visits a GP or an urgent care service with red, sticky eyes and discharge; a clinician diagnoses bacterial conjunctivitis and issues a prescription for topical antibiotic therapy.
Contact‑lens wearers, severe presentations or suspected corneal involvement often lead to a fluoroquinolone such as Ocuflox rather than chloramphenicol.
Patients commonly call pharmacies asking about Ocuflox price UK or whether an ofloxacin eye drops product is in stock.
Phone queries often mention worry about driving after treatment because of transient blurred vision, or concern about contact‑lens use during therapy.
Online services increase access but will require an uploaded prescription or an online consultation for validation before dispatch.
| Supply Channel | Typical Access | Patient Notes |
|---|---|---|
| NHS Prescription | Standard route; electronic prescriptions common | May incur charge in England; exemptions in devolved nations |
| Private Prescription | Issued by private clinics or private GP; patient pays | Useful out of hours; cost varies by clinic and brand |
| Online Pharmacy | Upload/validate prescription or complete online consultation | Convenient for repeat or remote supply; discreet delivery options |
Product Snapshot & Key Specifications
Core Product Identifiers
The international nonproprietary name is Ofloxacin, presented in some texts as Ofloxacin.
The ATC code is S01AE01, placing it among ophthalmological fluoroquinolones.
Typical branded products in the United Kingdom are Ocuflox and Exocin supplied as 0.3% ophthalmic solution.
Indications include bacterial conjunctivitis and bacterial corneal ulcer as stated in product literature.
Packaging, Formulation & Excipients
Most commercial packs are 5 mL LDPE multi‑dose bottles containing 3 mg/mL (0.3%) ophthalmic solution.
Preserved versions may include benzalkonium chloride; preservative‑free single‑dose units are co‑marketed for hospital or sterile use.
Storage guidance is to keep unopened bottles at 15–25°C and to discard within 28 days of opening.
Ofloxacin is a fluoroquinolone ophthalmic anti‑infective with good gram‑negative activity and corneal penetration.
| Brand | Concentration | Pack Size | Preservative |
|---|---|---|---|
| Ocuflox | 0.3% (3 mg/mL) | 5 mL multi‑dose | May contain benzalkonium chloride / available preservative‑free |
| Exocin | 0.3% (3 mg/mL) | 5 mL multi‑dose | Preserved versions and single‑dose units marketed |
Key Selling Points:
- Fast symptomatic relief in bacterial conjunctivitis.
- Broad gram‑negative coverage and suitable corneal penetration for ulcers.
- Available as multi‑dose or preservative‑free single‑dose units for sterile use.
Indications & Practical Usage Scenarios
When To Recommend (Community Pharmacy)
Recommend Ocuflox for patients with confirmed or strongly suspected bacterial conjunctivitis when a topical fluoroquinolone is appropriate.
Consider ofloxacin particularly for contact‑lens wearers, suspected gram‑negative involvement, or where prior chloramphenicol therapy has failed.
For paediatric patients aged ≥1 year, the same topical dosing schedules apply when a clinician has prescribed ofloxacin.
Pharmacists should reinforce contact‑lens removal during treatment and discuss possible stinging on instillation.
When To Refer Urgently
Urgent referral to ophthalmology or emergency services is required for severe eye pain, reduced visual acuity, marked photophobia, or clinical signs suggesting corneal ulceration.
Also refer if there is failure to improve after 48–72 hours of appropriate topical therapy, or if eyelid adhesions and severe purulent discharge develop.
Corneal ulcers require culture‑guided therapy and close follow‑up; pharmacists should advise patients to seek prompt ophthalmic review rather than attempting self‑treatment.
- Bacterial Conjunctivitis →
- Administer topical antibiotic per prescription; monitor for improvement within 48–72 hours.
- Contact‑Lens Associated Red Eye →
- Prefer broad gram‑negative coverage (eg. ofloxacin) and urgent ophthalmology if keratitis suspected.
- Corneal Ulcer →
- Immediate ophthalmic referral and intensive topical therapy under specialist supervision.
Dosage & Administration (Practical Table + Counselling)
Typical Dosing Schedules
| Condition | Typical Adult Dose | Treatment Duration |
|---|---|---|
| Bacterial Conjunctivitis | 1–2 drops into affected eye(s) every 2–4 hours for 2 days, then every 4–6 hours | Up to 7 days |
| Corneal Ulcer | 1–2 drops every 30–60 minutes on day 1, then hourly reducing per response | Up to 14 days or per specialist advice |
Paediatric, Elderly & Missed Dose Guidance
Children aged 1 year and older may be treated with the same topical regimens as adults when prescribed by a clinician.
Infants under 1 year have not established safety data and use is not recommended without specialist advice.
Elderly patients usually do not need dose adjustment for topical therapy but monitor for increased ocular sensitivity.
If a dose is missed, apply when remembered and do not double up at the next scheduled time.
For suspected overdose rinse the eye with water; systemic toxicity is rare with ophthalmic preparations.
Practical Instillation Steps:
- Wash hands thoroughly before use.
- Tilt the head back and pull the lower eyelid to form a small pocket.
- Instil one drop, close the eye for 1–2 minutes and press the medial canthus to reduce systemic absorption.
- Wait at least five minutes before applying other eye drops.
Safety, Contraindications & Monitoring
Absolute & Relative Contraindications
Absolute contraindications include known hypersensitivity to ofloxacin or other quinolones and allergy to excipients such as benzalkonium chloride.
Relative cautions include a history of tendon disorders associated with quinolones, pregnancy and lactation where use should be limited to cases where benefits outweigh risks, and infants under 1 year due to lack of safety data.
Monitoring And Special Populations
Patients with corneal ulcers need specialist follow‑up, culture results and healing checks to ensure resolution and to guide escalation or change of therapy.
Advise removal of contact lenses during therapy and for at least 15 minutes after each instillation for preserved formulations.
Alert prescribers and arrange referral if ocular surface toxicity, increasing pain or worsening vision occur during treatment.
- Check allergy history for quinolones and preservatives before dispensing.
- Document age and pregnancy/breastfeeding status when validating prescriptions.
- Use preservative‑free units for patients with severe ocular surface disease where available.
Side Effects, Incidence And Counselling
Common Local Adverse Effects
Common local reactions include transient stinging or burning on instillation, ocular redness, dryness, eyelid irritation and brief blurred vision.
Photophobia and mild discomfort may occur but typically resolve without stopping treatment.
Rare / Serious Reactions & Reporting
Serious allergic reactions are rare but require immediate cessation and urgent medical attention if swelling, hives or breathing difficulty occur.
Systemic adverse events are uncommon with topical use, although systemic fluoroquinolone safety warnings apply in the event of significant systemic exposure.
Advise patients not to drive or operate machinery if vision is blurred after instillation.
Encourage reporting of suspected significant adverse reactions via the MHRA Yellow Card scheme.
| Common Effects | Serious Effects |
|---|---|
| Stinging, burning, redness, blurred vision | Anaphylaxis, severe swelling, marked vision loss |
Counselling Points: Expect short‑lived stinging; avoid contact lenses; seek urgent review for severe pain or sudden vision change.
Interactions & Concomitant Therapies
Eye‑Drop Specific Interactions
Wait at least five minutes between different ophthalmic medicines to avoid washout and reduced efficacy.
Preservative‑containing drops with benzalkonium chloride may reduce contact‑lens tolerance and should not be used while lenses are worn.
Topical use minimises systemic interactions, but concurrent use of multiple topical quinolones should be documented and justified.
Systemic Drug Interaction Considerations
Systemic interactions are minimal because topical absorption is low, though caution is reasonable where multiple fluoroquinolone exposures occur.
Prior topical antibiotic use can reduce culture yield in corneal infections, so inform ophthalmology teams about recent drops used when arranging cultures.
| Topical Consideration | Systemic Consideration |
|---|---|
| Wait 5 minutes between drops; avoid lens wear with preserved drops | Systemic interactions rare; cumulative fluoroquinolone exposure theoretical risk |
Evidence, Efficacy & Key Clinical Data
Efficacy For Conjunctivitis & Corneal Ulcer
Topical ofloxacin achieves bacterial eradication in many cases of bacterial conjunctivitis with symptomatic improvement often within 48–72 hours.
For corneal ulcers, intensive topical ofloxacin regimens provide corneal penetration appropriate for treating many pathogens under ophthalmic supervision.
Key Trial Summaries & Limitations
Clinical trials and regulatory submissions demonstrate efficacy versus comparators for conjunctivitis and support use in corneal infections when guided by culture results.
Limitations include variable trial quality, changing regional resistance patterns and the need to follow local susceptibility data when choosing empirical therapy.
| Indication | Evidence Strength | Typical Outcome |
|---|---|---|
| Bacterial Conjunctivitis | Good | Rapid bacterial eradication and symptom relief within 48–72 hours |
| Corneal Ulcer | Moderate (specialist‑managed) | Reduction in culture positivity and healing with close follow‑up |
Pharmacists should link patients and prescribers to MHRA product literature and national guidance for the most current recommendations.
Comparative Products & Switching Guidance
Main Competitors And Differentiators
Competitors include ciprofloxacin, moxifloxacin, gatifloxacin, levofloxacin (systemic use mainly), tobramycin and chloramphenicol.
Differentiators are spectrum of activity, corneal penetration, dosing frequency, preservative status and cost.
Moxifloxacin and gatifloxacin may offer extended gram‑positive coverage in some settings, while ciprofloxacin is another commonly used topical fluoroquinolone.
When To Switch Or Escalate Therapy
Consider switching if there is no clinical improvement after 48–72 hours, or earlier if signs point to corneal involvement or worsening infection.
Culture and sensitivity testing should guide escalation to alternative topical agents or systemic therapy under ophthalmology advice.
| Drug | Typical Spectrum | Typical Dosing | Preservative Options |
|---|---|---|---|
| Ofloxacin (Ocuflox) | Broad gram‑negative, good corneal penetration | 1–2 drops q2–4h (conjunctivitis); intensive for ulcers | Preserved and preservative‑free options |
| Chloramphenicol | Broad‑spectrum, non‑quinolone | Hourly or q2h depending on product | Usually preserved |
Purchasing, NHS Vs Private Supply & Pricing
Prescription Processes & Electronic Prescribing
Ocuflox is classified as prescription only and standard NHS electronic prescriptions are commonly used in the UK for community pharmacy dispensing.
Private prescriptions and online consultations are alternative routes; online pharmacies will validate uploaded prescriptions or keep a consultation record when dispensing.
In our online pharmacy, exocin is available without a prescription, with discreet delivery to United Kingdom in 5–14 days.
Price Drivers And Regional Differences
Price factors include brand versus generic, pack type (multi‑dose vs single‑dose), and whether the supply is via NHS prescription or private purchase.
Scotland, Wales and Northern Ireland have prescription exemptions that can eliminate out‑of‑pocket charges, whereas in England patients commonly pay the NHS prescription charge unless exempt.
| Route | Cost Factors | Prescription Requirement |
|---|---|---|
| NHS | Standard prescription charge in England; exemptions in devolved nations | Valid NHS prescription required |
| Private | Consultation and medication fees; brand choice affects price | Private prescription required |
| Online Pharmacy | Consultation fees, delivery cost, brand selection | Prescription upload/validation or online consultation |
Dispensing, Labelling & Pharmacy Workflow Notes
Mandatory Labelling & Patient Information
Check the prescription specifies 0.3% ofloxacin and confirm the patient is aged ≥1 year where applicable.
Labels must state “For ophthalmic use only”, dosing instructions, frequency and patient‑specific advice such as contact‑lens removal.
Document batch and expiry details and advise on the 28‑day in‑use discard for multi‑dose bottles unless the product literature specifies otherwise.
Storage And Stock Management
Store unopened bottles at 15–25°C away from direct light and do not freeze.
Keep preservative‑free single‑dose units separate from preserved multi‑dose bottles to prevent dispensing errors.
For hospital or sterile settings supply single‑use units where required and track stock for recalls or shortages.
Dispensing Flow:
- Validate prescription and allergy history.
- Select correct product (concentration, preservative status).
- Label with “For ophthalmic use only” and patient instructions.
- Counsel on instillation, contact‑lens advice and when to seek review.
Prescriber & Pharmacist Checklist
Pre‑Prescription Considerations
Confirm the indication supports a fluoroquinolone: contact‑lens wearer, severe infection, or corneal involvement.
Check for quinolone or preservative allergies and verify patient age, pregnancy and breastfeeding status.
Decide between preservative‑free single‑dose units and preserved multi‑dose bottles based on ocular surface health.
Counselling & Follow‑Up Prompts
Explain the dosing schedule, instillation technique and the need to remove contact lenses during treatment.
Arrange or advise follow‑up if symptoms do not improve within 48–72 hours and urge urgent review for severe pain or vision loss.
Record lot/batch in the patient record and advise on discard within 28 days when applicable.
- Check allergies, age and pregnancy status before supply.
- Provide a printed or electronic patient instruction slip with dosing calendar.
- Ensure online consultation records are stored when dispensing remotely.
Patient Leaflets, Adherence Tips & Self‑Care
Simple Instillation Technique & Calendars
Provide stepwise instructions: wash hands; tilt head back; pull lower lid; instil one drop; close the eye for 1–2 minutes; press the inner corner to limit systemic absorption.
Recommend phone reminders, dosing calendars or pharmacist follow‑up calls to improve adherence.
Non‑Pharmacological Measures And Red‑Flag Signs
Advise patients not to rub their eyes, to avoid sharing towels, and to stop contact‑lens wear until the infection clears.
Self‑care for crusting may include warm compresses, but red‑flag signs such as severe pain, sudden vision loss, marked photophobia or increasing discharge warrant immediate review.
FAQs often include “Can I drive?” — advise refrain from driving if vision is blurred after instillation.
Offer a printable leaflet and a simple adherence calendar for patients to mark dosing times and symptoms.
Regulatory, Manufacturing & Supply Information
INN, ATC And Regulatory Status
The INN is Ofloxacin and the ATC classification is S01AE01 for ophthalmic fluoroquinolones.
Ocuflox and Exocin are registered in multiple national markets and the product is Rx‑only under MHRA oversight in the UK.
The US FDA has approved ofloxacin ophthalmic formulations under NDA# 020405 and various national registrations exist across the EU and other regions.
Manufacturers, Packaging & Supply Chain Notes
Major global suppliers include Allergan (AbbVie), Santen, Dr. Reddy’s and Alcon, with local generics available regionally.
Packaging is usually LDPE multi‑dose bottles of 5 mL, and single‑dose preservative‑free units are supplied for sterile settings.
Pharmacists should monitor MHRA supply alerts for batch recalls and shortages and register for manufacturer updates where possible.
- INN →
- Ofloxacin (ATC S01AE01)
- Manufacturers →
- Allergan (AbbVie); Santen; Dr. Reddy’s; Alcon; local generics
- Regulatory Note →
- Rx‑only with national SPC/PIL as authoritative references
Delivery Across United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | Greater London | 5–7 days |
| Birmingham | West Midlands | 5–7 days |
| Manchester | Greater Manchester | 5–7 days |
| Glasgow | Scotland | 5–7 days |
| Edinburgh | Scotland | 5–7 days |
| Leeds | West Yorkshire | 5–7 days |
| Liverpool | Merseyside | 5–7 days |
| Bristol | South West England | 5–9 days |
| Sheffield | South Yorkshire | 5–9 days |
| Newcastle Upon Tyne | North East England | 5–9 days |
| Belfast | Northern Ireland | 5–7 days |
| Cardiff | Wales | 5–7 days |
| Plymouth | Devon | 5–9 days |
| Norwich | East of England | 5–9 days |
Final Notes For Pharmacy Teams
When validating an Ocuflox or Exocin prescription confirm INN, concentration and preservative status against the prescription.
Explain instillation technique, likely transient stinging and the need to remove contact lenses during treatment.
Advise patients to report severe reactions and to use the MHRA Yellow Card scheme for suspected serious adverse events.
Keep local resistance trends and ophthalmology advice in mind when recommending empirical therapy and escalate promptly if there is no response within 48–72 hours.