Liothyronine
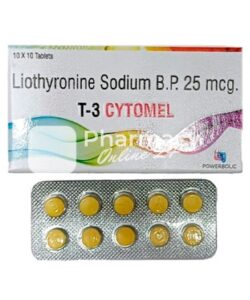
In brief
- In our pharmacy, you can buy liothyronine without a prescription, with delivery in 5–14 days throughout the United Kingdom. Discreet and anonymous packaging.
- Liothyronine is used to treat hypothyroidism and certain cases requiring rapid thyroid hormone replacement (eg, myxoedema coma); it is synthetic triiodothyronine (T3) that acts on nuclear thyroid hormone receptors to increase metabolic rate and regulate growth and development.
- The usual oral dose for adults starts at 5–25 µg daily, typically increased in 5–10 µg increments to a maintenance range of about 25–75 µg daily (some patients may require up to ~100 µg/day); dose and titration depend on age, cardiac status and clinical response.
- Administered orally as tablets; an injectable form is available for intravenous use in hospital settings (eg, myxoedema coma).
- Liothyronine begins to raise serum T3 levels within 2–4 hours after oral administration, so biochemical effects are relatively rapid.
- The clinical duration of action is shorter than levothyroxine, with effects typically lasting around 24 hours (half‑life approximately one day), often requiring once‑daily dosing or divided doses in some patients.
- Avoid excessive alcohol; alcohol can worsen underlying conditions and may increase the risk of adverse effects (patients with alcohol‑related liver disease should use cautiously and under medical advice).
- The most common side effects are palpitations, tremor, nervousness/insomnia and heat intolerance; these reflect excess thyroid hormone and dose adjustment may be required.
- Would you like to try liothyronine without a prescription?
Market Realities And Patient Experiences With Liothyronine
Basic Liothyronine Information
- INN (International Nonproprietary Name): Metformin
- Brand Names Available In United Kingdom: Metformin Hydrochloride, Sukkarto SR
- ATC Code: A10BA02
- Forms & Dosages: Film-coated tablets 250mg, 500mg, 850mg, 1000mg; extended-release 500–1000mg; oral solution 500mg/5mL; sachets (usually 1000mg)
- Manufacturers In United Kingdom: Sanofi, Merck, Teva Pharmaceuticals, Sun Pharma, Cipla, Intas, Torrent, Mylan, Hexal
- Registration Status In United Kingdom: MHRA approved as prescription-only medicine
- OTC / Rx Classification: Prescription only (Rx)
Availability, Cost And Real-World Patient Stories
Is liothyronine easy to find in UK pharmacies?
Availability varies across the UK and many pharmacies carry limited stock due to specialist prescribing patterns.
Patients commonly report quick symptom change when starting T3, most often improved energy and clearer thinking within days.
Equally common are dose-related side effects such as palpitations, anxiety and sleep disturbance when dosing is not well managed.
NHS prescribing is usually restrictive and levothyroxine remains first-line, so liothyronine is often only issued after specialist review or under local shared-care agreements.
Private prescriptions and online clinics have increased demand and have pushed some patients to seek private supply or specialist review when GP access is slow.
These supply pressures influence buying behaviour and pharmacist counselling as patients sometimes request urgent private supply rather than waiting for NHS pathways.
Unlike metformin, which is widely generic and abundantly stocked, liothyronine tends to be stocked in smaller quantities and may be special-ordered.
| Supply Route | Typical Cost / Note | Typical Lead Time |
|---|---|---|
| NHS Prescription | Usually covered on repeat prescription where approved; subject to local formulary restrictions | 1–7 days (may require specialist authorisation) |
| Private Prescription | Patient pays privately; cost varies by pharmacy and pack size (higher than levothyroxine) | Same day to 7 days, depending on stock |
| Online Clinics / Private Retailers | Variable pricing and verification processes; pharmacists must confirm legitimacy | 2–14 days depending on verification and delivery |
What Liothyronine Is (Drug Basics)
Mechanism, INN, Legal Status In The UK
What does liothyronine actually do?
Liothyronine, listed as liothyronine sodium (INN liothyronine), is the synthetic active thyroid hormone T3.
The drug acts on nuclear thyroid receptors to increase metabolic rate, raise thermogenesis and change gene transcription in target tissues.
In clinical practice it is reserved for situations where rapid onset or direct T3 activity is required because levothyroxine (T4) usually converts peripherally to T3.
Liothyronine is a prescription-only medicine (POM) in the United Kingdom and regulated by the MHRA.
Many available brands are specialist or limited-license products and pack sizes tend to be small blisters with microgram tablets.
Compared with metformin, which has wide generic availability and many pack sizes globally, liothyronine supply in community settings is more constrained.
- INN: Liothyronine (liothyronine sodium)
- Salt Form: Sodium salt of triiodothyronine (T3)
- Common Brand Names: Varies by supplier and not specified here
- Regulatory Status: Prescription-only (POM), MHRA regulated
Indications And Common Clinical Uses
Approved Indications, Specialist Uses And Off-Label Scenarios
When is liothyronine used clinically?
Primary approved use is for hypothyroidism when T3 therapy is specifically indicated or when rapid action is needed.
Examples include patients with reduced peripheral conversion of T4 to T3, or those after thyroidectomy who require tailored replacement.
In hospital practice intravenous liothyronine may be used in myxoedema coma as part of critical care protocols.
Short-term liothyronine is sometimes used to accelerate metabolic response under specialist supervision.
Off-label roles can include adjunctive treatment in selected, treatment-resistant depression cases or persistent symptoms despite normal thyroid function tests, but such use must be specialist-led and monitored.
- Approved indications: Specific cases of hypothyroidism needing T3
- Specialist inpatient uses: Myxoedema coma (IV liothyronine)
- Off-label examples: Adjunct for selected depression cases or persistent symptomatic patients — only with specialist oversight
Available Preparations, Strengths And Packaging
Typical UK Presentations And Manufacturer Notes
What preparations of liothyronine are commonly supplied?
Oral liothyronine tablets are supplied in microgram strengths — commonly 5 µg, 10 µg and 20 µg depending on manufacturer.
Injectable IV liothyronine is available for hospital use in emergencies such as myxoedema coma or when enteral absorption is not possible.
Packs are usually small blister cards because specialist prescribing and frequent monitoring reduce the need for large counts.
Storage is at room temperature, away from moisture and light, and packs should be kept in original packaging to avoid confusion with other microgram-strength tablets.
| Strength | Typical Pack Size | Route |
|---|---|---|
| 5 µg | Small blister packs (e.g. 28 tablets; varies) | Oral |
| 10 µg | Small blister packs (e.g. 28 tablets; varies) | Oral |
| 20 µg | Small blister packs (fewer tablets) | Oral |
| IV Preparation | Hospital vials; specialist stock | Intravenous |
Manufacturer Notes
Because liothyronine is specialist-led, community pharmacies often hold minimal stock and will order to patient-specific prescriptions.
Pharmacists should place special orders promptly and advise patients about expected lead times and any supply volatility.
Dosing: Initiation, Titration And Maintenance
Practical Regimens And UK Prescribing Norms
How should dosing be started and adjusted?
Start low and titrate slowly, particularly in older patients or those with cardiac risk.
Typical adult initiation for symptomatic patients is 5–10 µg daily, with increments of 5–10 µg every one to three weeks guided by symptoms and thyroid function tests.
Maintenance doses frequently fall in the 25–75 µg/day range and are often split between morning and early afternoon because of liothyronine’s short half-life.
Young, otherwise well patients may require higher doses tailored individually, but avoid abrupt large increases due to cardiac risk.
- Starting Doses: 5–10 µg daily for at-risk patients; higher for low-risk younger adults
- Titration Schedule: Increase by 5–10 µg every 1–3 weeks while monitoring symptoms and TFTs
- Maintenance: Often 25–75 µg/day, commonly divided
Elderly patients and those with ischaemic heart disease require specialist oversight and slower titration with ECG monitoring where indicated.
Switching From Levothyroxine — Combination Therapy (T4/T3)
How Pharmacists Support Switching And Rationale
Why might a clinician switch to combination T4/T3 therapy?
Some patients report persistent symptoms on levothyroxine despite normal blood tests, prompting a specialist trial of liothyronine alone or in combination with levothyroxine.
Combination approaches vary; clinicians may replace a small portion of levothyroxine with liothyronine to provide a physiological mix of T4 and T3.
A pragmatic approach is to introduce liothyronine 5–10 µg while reducing levothyroxine appropriately and rechecking TSH, free T4 and free T3 at around six to eight weeks.
| Scenario | Example Adjustment | Monitoring |
|---|---|---|
| Replace small T4 fraction | Introduce 5 µg liothyronine, reduce levothyroxine by clinician-calculated amount | TFTs at 6–8 weeks; symptom review |
| Trial of T3 alone | Specialist-led, low initial dose with close follow-up | Frequent TFTs and cardiac assessment if required |
Pharmacists should confirm specialist prescription, advise on split dosing, and counsel patients to report palpitations, chest pain or severe anxiety immediately.
Safety, Contraindications And Adverse Effects
Key Warnings For Pharmacy Teams And Patients
What safety issues should be front of mind?
Common dose-related adverse effects include palpitations, tremor, insomnia, anxiety, heat intolerance and weight loss.
Serious risks arise from excess thyroid hormone and include precipitation of angina, arrhythmias and accelerated osteoporosis with long-term oversupply.
Absolute contraindications include untreated adrenal insufficiency, thyrotoxicosis and recent acute myocardial infarction or unstable ischaemic heart disease.
Liothyronine should be used cautiously in elderly patients and those with known cardiac disease; specialist review and ECG monitoring may be necessary.
- Mild Side Effects: Tremor, nervousness, sweating, insomnia
- Serious Risks: Arrhythmia, angina, long-term bone loss
- Red Flags: Chest pain, severe palpitations, sudden shortness of breath — seek urgent care
Drug Interactions And Monitoring Essentials
Clinically Important Interactions And TFT Follow-Up
Which interactions are clinically relevant for liothyronine?
Liothyronine potentiates oral anticoagulants such as warfarin, increasing bleeding risk and often reducing required anticoagulant dose; INR should be checked after initiation or dose changes.
The drug may change insulin and oral hypoglycaemic needs, so glucose control should be reviewed when thyroid dose changes.
Amiodarone and lithium impact thyroid physiology and may complicate dosing decisions; liaison with the prescriber is advised.
Calcium, iron supplements and bile acid sequestrants can reduce oral absorption; advise spacing these by about four hours from liothyronine doses.
- Key interacting classes: Anticoagulants, insulin/antidiabetics, amiodarone, lithium, calcium/iron supplements
- Monitoring timetable: Baseline TFTs, repeat 6–8 weeks after any dose change, then individualised checks
- Pharmacist actions: Flag INR checks, counsel on spacing supplements, confirm medication list for interactions
Pharmacy Purchase Routes: NHS, Private And Online
How UK Patients Obtain Liothyronine And Pricing Realities
How do patients get liothyronine in the UK?
Most liothyronine is prescribed via GP or specialist and dispensed through NHS pharmacies, but many NHS pathways restrict T3 so specialist approval is common.
Private clinics and online prescribers offer private prescriptions and have increased supply requests, but pharmacists must verify the legitimacy of private and remote prescriptions.
Major pharmacy chains may hold some stock, yet availability is variable and community pharmacies commonly order to patient-specific prescriptions.
Compared with metformin, which is generically abundant and low-cost, liothyronine supply is more specialist-led and can incur higher private costs and longer lead times.
| Route | Typical Stock / Notes | Lead Time |
|---|---|---|
| NHS Dispense | Subject to local formulary and specialist approval; often limited stock | 1–7 days |
| Private Prescription | Readily dispensed if prescription valid; patient pays | Same day to 7 days |
| Online Purchase | Verification required; variable pricing; pharmacists must confirm identity of prescriber | 2–14 days |
Note: In our online pharmacy, liothyronine is available without a prescription, with discreet delivery to United Kingdom in 5-14 days.
Counselling Points For Patients (How To Take, Side-Effect Recognition)
Clear, Practical Advice Pharmacists Must Give
What practical advice should patients receive at the counter?
Take liothyronine consistently at the same time each day, usually in the morning; if taken twice daily, the second dose should be mid-afternoon to avoid insomnia.
Space liothyronine from calcium and iron supplements by three to four hours to preserve absorption.
If a dose is missed, take it when remembered unless it is close to the next scheduled dose — do not double up.
Advise patients to watch for signs of excess thyroid such as palpitations, chest pain, marked anxiety or severe tremor and to seek urgent care for chest pain or severe arrhythmia.
Store medicine in its original packaging, away from moisture and heat, and return unused medicines to the pharmacy for safe disposal.
- Do: Take morning dose consistently, report palpitations or insomnia
- Don’t: Take late afternoon doses that may cause sleep problems or double missed doses
- When To Call GP: New chest pain, severe breathlessness, fainting or sudden worsening symptoms
Laboratory Monitoring And Interpreting Results
TSH, Free T4, Free T3 Targets And Practical Timelines
How should clinicians and pharmacists interpret thyroid tests on liothyronine?
Liothyronine increases circulating T3 quickly and may suppress TSH even when peripheral T4 appears normal, so interpretation must be clinical as well as biochemical.
Baseline tests should include TSH, free T4 and free T3 prior to a dose change, and repeat testing at about six to eight weeks after any adjustment.
Because T3 equilibrates faster than T4, symptoms may change earlier than lab values; however allow the standard interval for meaningful TFT changes before major dose decisions.
Avoid aiming for sustained TSH suppression in most patients because that raises risk of atrial fibrillation and osteoporosis, particularly in older adults.
| Test | When | Action If Abnormal |
|---|---|---|
| Baseline TSH, Free T4, Free T3 | Before starting or changing dose | Guide starting dose and inform monitoring plan |
| Follow-Up | 6–8 weeks after change; then individualised (6–12 months if stable) | Adjust dose to relieve symptoms without suppressing TSH inappropriately |
Use In Pregnancy, Breastfeeding And Fertility
Risks, Guidance And Prescribing Notes
Is liothyronine safe in pregnancy?
Pregnancy requires effective thyroid replacement because maternal hypothyroidism affects foetal development, and levothyroxine is generally preferred due to steady levels and extensive data.
Liothyronine crosses the placenta and is reserved for specialist use in pregnancy when levothyroxine is inadequate or rapid action is needed.
For breastfeeding, liothyronine appears in milk in small amounts and specialist review should balance maternal benefit and infant exposure.
In fertility care, adequate thyroid replacement supports conception and early pregnancy; clinicians adjust therapy preconception and monitor closely.
- Pregnancy checklist: Prefer levothyroxine; consider liothyronine only with specialist advice
- Breastfeeding: Specialist oversight recommended; monitor infant if use is necessary
- Fertility: Ensure euthyroid state before conception; frequent monitoring in early pregnancy
Special Clinical Scenarios (Myxoedema Coma, Paediatrics, Cardiac Disease)
Emergency Vs Routine Management And Pharmacy Role
What changes in emergency or specialised contexts?
Myxoedema coma is a medical emergency treated in hospital with intravenous liothyronine as part of critical care protocols; these preparations are hospital-only and ordered through hospital pharmacy.
Paediatric use of liothyronine is uncommon as first-line therapy and requires paediatric endocrinology input for dosing and monitoring.
In patients with cardiac disease, liothyronine can precipitate ischaemia or arrhythmia and cardiology input is recommended before initiation or escalation.
Pharmacists should confirm the stated indication and ensure specialist oversight for these scenarios and contact the prescriber if uncertainty exists.
- Emergency dosing (high-level): IV liothyronine under critical care — hospital supply only
- Paediatric considerations: Specialist paediatric endocrinologist involvement essential
- Cardiac disease: Cardiology review recommended before starting or increasing dose
Storage, Disposal, Missed Dose And Overdose Management
Practical Pharmacy Notes And Patient Leaflets
How should liothyronine be stored and what to do in overdose?
Store at room temperature, away from light and moisture, and keep tablets in their original blister to avoid confusion between microgram strengths.
Return unused packs to the pharmacy for safe disposal; do not flush medications down the toilet.
If a dose is missed, the patient should take it when remembered unless it is near the next dose — do not double the next dose.
Overdose symptoms include palpitations, chest pain, severe tremor, marked anxiety and fever and require urgent medical attention.
- Storage checklist: Room temperature, original pack, away from children and pets
- Emergency actions for overdose: Call emergency services for chest pain or severe symptoms
- Patient leaflet items: Dosing times, spacing supplements, red-flag symptoms, disposal instructions
Comparative Regulatory And Market Context (Liothyronine Vs Metformin)
What The Pharmacy Team Should Know About Supply Patterns And Classification
How does liothyronine compare with a mass-market agent like metformin?
Metformin (ATC A10BA02) is widely generic, produced by many manufacturers and available in multiple strength and pack options worldwide, making it broadly available and cost-efficient.
Liothyronine, by contrast, is a specialist endocrine medicine with limited pack sizes, fewer manufacturers in routine community markets and more constrained availability in pharmacies.
Both drugs are prescription-only in the UK, but metformin’s mass-market status supports steady supply and low cost while liothyronine often requires special ordering and may have higher private costs.
| Feature | Liothyronine | Metformin (Reference) |
|---|---|---|
| INN | Liothyronine | Metformin |
| ATC / Class | Endocrine — thyroid replacement (not specified ATC here) | A10BA02 — Biguanide |
| Typical Pack Sizes | Small blister packs of microgram tablets | Multiple tablet sizes and larger packs worldwide |
| Indications | Hypothyroidism when T3 required; specialist use | Type 2 diabetes; first-line oral antidiabetic |
| Supply Notes | Specialist-led, variable stock, potential supply pressure | Widely available generics, stable supply |
Pharmacy teams should flag longer supply times for liothyronine, verify specialist authorisation, and counsel patients on monitoring differences and interaction profiles compared with common generics like metformin.
SEO & Product-Page Elements For A Pharmacy Listing
What Content Converts And Meets NHS/Patient Expectations
What details build trust on a product page for liothyronine?
Essential elements are clear prescribing status (POM), exact pack size and strength, concise dosing examples with “seek specialist advice” disclaimers, monitoring requirements and contraindications.
Display side-effect highlights, price comparison between NHS and private options, current stock and lead times, and a verified pharmacist contact button for clinical queries.
Use structured data and patient-friendly FAQs to aid SEO and build confidence; avoid clinical overclaiming and always link patients to MHRA or specialist guidance when appropriate.
- Mandatory legal statements: POM, always check with prescriber before changes
- Quick-read counselling bullets: How to take, spacing supplements, red-flag symptoms
- FAQ examples: How quickly T3 works; what to do about missed doses; when to seek urgent care
Elements such as a dosage calculator snapshot, stock/lead-time badge and verified pharmacist Q&A improve conversion while meeting NHS and patient expectations.
Delivery Across United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 5-7 days |
| Birmingham | England | 5-7 days |
| Manchester | England | 5-7 days |
| Leeds | England | 5-7 days |
| Glasgow | Scotland | 5-7 days |
| Edinburgh | Scotland | 5-7 days |
| Bristol | England | 5-7 days |
| Newcastle | England | 5-9 days |
| Sheffield | England | 5-9 days |
| Liverpool | England | 5-9 days |
| Belfast | Northern Ireland | 5-9 days |
| Cardiff | Wales | 5-9 days |
| Norwich | England | 5-9 days |
| Exeter | England | 5-9 days |
Final Notes For Pharmacy Teams
Practical Reminders
Always verify the prescriber and the stated indication for liothyronine before dispensing.
Explain dosing timing and the need to space calcium and iron supplements, and flag INR monitoring where patients are anticoagulated.
Be ready to order small specialist packs and communicate likely lead times to patients to reduce anxiety and prevent gaps in therapy.
Keep clear patient leaflets covering missed-dose advice, overdose red flags and storage/disposal instructions with every dispense.
When in doubt, contact the specialist prescriber for clarity and document any advice given in the patient record.