Salazopyrin
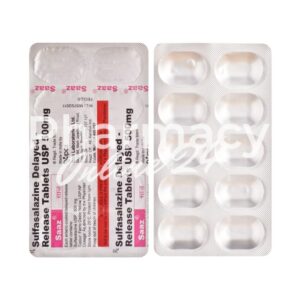
In brief
- In our pharmacy, you can buy Salazopyrin without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Salazopyrin (sulfasalazine) is used to treat and maintain remission in ulcerative colitis and to manage rheumatoid arthritis and juvenile idiopathic arthritis; it is metabolised in the bowel to 5‑aminosalicylic acid and sulfapyridine, providing local anti‑inflammatory effects in the gut and systemic immunomodulatory activity.
- The usual dosage: ulcerative colitis adults 1–2 g/day initially and typically 2 g/day for maintenance (severe up to 4 g/day); rheumatoid arthritis adults start ~0.5 g/day and titrate to ~2 g/day (max ~3 g/day); children ≥6 years 30–50 mg/kg/day (up to ~2 g/day).
- Form of administration: oral tablets (immediate‑release 500 mg and delayed‑release EN‑tabs 500 mg); take with food and a full glass of water and split the daily dose into 2–4 doses to improve tolerance.
- The effect of the medication on disease activity is gradual: ulcerative colitis induction typically 3–6 weeks, and rheumatoid arthritis response often 6–12 weeks; some symptom relief may be noticed earlier.
- The duration of action per dose is approximately 8–12 hours (active metabolites have half‑lives in the order of several hours); clinical benefits are maintained only with continued daily dosing and may be long‑term for maintenance therapy.
- Do not consume excessive alcohol; alcohol can increase the risk of liver toxicity and may worsen gastrointestinal side effects — exercise caution and avoid heavy drinking while taking salazopyrin.
- The most common side effect is gastrointestinal upset (nausea, vomiting, abdominal pain); other common effects include headache, rash, reversible yellow‑orange discoloration of urine or skin, and mild haematological abnormalities.
- Would you like to try Salazopyrin without a prescription?
Legal status and availability in the UK
Salazopyrin is a prescription-only medicine (POM) in the UK.
In our online pharmacy, Salazopyrin is available without a prescription, with discreet delivery to the United Kingdom in 5‑14 days.
Basic salazopyrin information
- INN (international nonproprietary name): Sulfasalazine
- Brand names available in the United Kingdom: Salazopyrin, Salazopyrin EN‑tabs; generic sulfasalazine
- ATC code: A07EC01
- Forms and dosages: Immediate‑release 500 mg tablets; delayed‑release enteric‑coated EN‑tabs 500 mg; suspensions listed as rare in some territories
- Manufacturers in the United Kingdom: Pfizer (Salazopyrin) and generic manufacturers
- Registration status in the United Kingdom: authorised by the MHRA; prescription-only medicine (POM)
- OTC / Rx classification: Prescription-only medicine (POM)
The same medicine is often spoken of as sulfasalazine or by the brand name Salazopyrin.
Common worries include stomach upset, orange‑coloured urine and how long it takes to work for joint pain.
For rheumatoid arthritis the benefit can take six to twelve weeks to appear and that delay frustrates some people.
Taking tablets with food and splitting doses can reduce nausea.
Blood tests are needed to monitor for blood disorders, so the monitoring schedule should be followed.
Common patient questions: quick answers
- Will it upset my stomach? — Often at first; taking with food and splitting doses usually helps.
- How long until I feel better? — For RA expect 6–12 weeks; for UC induction effects can appear in weeks but maintenance is longer.
- Will my urine turn orange? — Yes, reversible yellow‑orange discolouration can occur and is harmless.
- Is it safe in pregnancy? — Discuss with your prescriber; specialist advice is recommended.
Typical symptom timeline
Week 0–2: possible GI upset and headache.
Week 3–6: early improvement for some UC symptoms; monitoring blood tests commonly scheduled.
Week 6–12: RA patients may notice reduced joint stiffness and pain.
Product snapshot — what salazopyrin (sulfasalazine) is
Active ingredient and classification
Salazopyrin is the trade name often used for preparations of the INN sulfasalazine.
The ATC code is A07EC01 which places it among intestinal anti‑inflammatory agents.
Common brand names include Salazopyrin and Salazopyrin EN‑tabs.
Typical pharmaceutical forms are immediate‑release 500 mg tablets and delayed‑release 500 mg EN‑tabs.
Salazopyrin is prescription only and is licensed for ulcerative colitis and rheumatoid arthritis, including juvenile forms.
Salazopyrin is made by Pfizer; generic sulfasalazine is also available.
Quick product summary
- INN: Sulfasalazine
- ATC: A07EC01
- Forms: Immediate‑release 500 mg tablets; Delayed‑release (EN‑tabs) 500 mg
- Prescription status: Prescription-only medicine (POM)
- Main manufacturers: Pfizer, generic manufacturers
Indications and practical use cases
Ulcerative colitis, rheumatoid arthritis, juvenile idiopathic arthritis, maintenance vs induction, off‑label notes
Sulfasalazine is licensed for induction and maintenance of ulcerative colitis in adults and for treatment of rheumatoid arthritis and juvenile idiopathic arthritis.
For ulcerative colitis the drug acts topically in the gut and dosing differs from systemic RA regimens.
For rheumatoid arthritis and JIA sulfasalazine is used as a disease‑modifying antirheumatic drug with a slow onset of action.
Typical patient profiles are adults with mild to moderate UC, RA patients who require a DMARD and children at least six years old for JIA using weight‑based dosing.
Duration of treatment varies: UC maintenance can be months to years if effective, while RA therapy is commonly sustained long‑term.
Patients who should discuss treatment with their prescriber include those who are pregnant or planning pregnancy, have liver or renal disease, or known G6PD deficiency.
Seek urgent review for rash, jaundice or signs of severe infection.
Indications: quick bullets
- Ulcerative colitis — induction and maintenance
- Rheumatoid arthritis — slow‑onset DMARD, often in combination therapy
- Juvenile idiopathic arthritis — children ≥6 years, weight‑adjusted dosing
- Induction
- Treatment aiming to control active disease; for UC this can be weeks.
- Maintenance
- Treatment to prevent relapse, often long‑term if tolerated and effective.
Dosage, titration and administration practicalities
Typical regimens per condition, titration advice, missed dose guidance
Ulcerative colitis in adults is typically started at 1–2 g per day in divided doses with maintenance around 2 g per day; severe disease may require up to 4 g daily.
For rheumatoid arthritis adults start at 0.5 g per day and titrate to about 2 g per day in two to four divided doses; maximum reported up to 3 g per day.
Juvenile RA dosing for children aged six and above is weight based at about 30–50 mg/kg/day up to approximately 2 g per day.
Administration tips include taking tablets with food and a full glass of water and splitting the daily dose into 2–4 portions to reduce gastrointestinal side effects.
If a dose is missed take it as soon as remembered unless the next dose is due soon and do not double up doses.
Start lower in the elderly and use caution or dose reduction in renal or hepatic impairment with close monitoring.
Enteric‑coated EN‑tabs can improve GI tolerability compared with immediate‑release tablets for some patients.
Typical dosage table
| Indication | Initial dose | Usual maintenance / notes |
|---|---|---|
| Ulcerative colitis (adults) | 1–2 g/day divided | Maintenance ~2 g/day; severe up to 4 g/day |
| Rheumatoid arthritis (adults) | Start 0.5 g/day, titrate | ~2 g/day in 2–4 doses; max ~3 g/day |
| Juvenile RA (≥6 years) | 30–50 mg/kg/day | Up to 2 g/day |
- Titration checklist: start low, increase gradually, split doses, schedule early blood tests.
Contraindications, precautions and who needs extra monitoring
Absolute vs relative contraindications, lab monitoring schedule
Absolute contraindications include known allergy to sulfonamides or salicylates, intestinal or urinary obstruction, porphyria and infants under two years old.
Relative contraindications requiring caution and monitoring include liver or kidney impairment, G6PD deficiency, blood dyscrasias, severe asthma or allergies and advanced age.
Pregnancy and breastfeeding require specialist discussion; prescribers should advise on risks versus benefits for each patient.
Baseline tests should include full blood count, liver function tests and renal function before starting therapy.
Repeat bloods are commonly done at two to four weeks after initiation and then approximately every three months or as advised by the specialist.
Patients with G6PD deficiency are at risk of haemolysis and should be offered alternatives where appropriate.
Screening and monitoring checklist
- Baseline CBC, LFTs and renal function before starting.
- Repeat bloods at 2–4 weeks, then every 3 months while stable.
- Assess pregnancy status where relevant and discuss with prescriber.
- Absolute
- Conditions where salazopyrin must not be used because of clear risk.
- Relative
- Conditions needing dose adjustment, extra monitoring or specialist review.
Side effects and what to do
Common, serious, reversible findings and when to escalate
Common mild adverse effects include nausea, vomiting, indigestion, abdominal pain, headache, dizziness and skin rash.
Patients may notice a harmless reversible yellow‑orange discolouration of urine or skin which should be explained to avoid alarm.
Reversible oligospermia and mild haematologic abnormalities are reported and usually resolve after stopping the medicine.
Serious but uncommon effects include agranulocytosis, severe hepatitis, pulmonary hypersensitivity and severe skin reactions such as Stevens‑Johnson syndrome.
Advise patients to stop the medicine and seek urgent GP or A&E if they develop fever, sore throat, unexplained bruising, jaundice, new rash or shortness of breath.
For non‑serious GI upset recommend taking with food, splitting doses or switching to enteric‑coated EN‑tabs as tolerated.
Common versus serious side effects
| Common | Serious |
|---|---|
| Nausea, headache, rash, orange urine | Agranulocytosis, severe hepatitis, pneumonitis, Stevens‑Johnson syndrome |
- Escalation checklist: stop drug and seek urgent care for fever, sore throat, jaundice, severe rash or breathing difficulty.
Drug interactions and laboratory monitoring details
Major interactions, co‑prescribing with other DMARDs, and required tests
Sulfasalazine can increase haematologic risk when used with other bone‑marrow suppressants such as methotrexate or azathioprine so close monitoring is essential.
There is an interaction with warfarin that can affect INR; more frequent monitoring of anticoagulation is advised when starting or stopping salazopyrin.
Drugs that affect folate pathways can modify activity and tolerability and should be reviewed with the prescriber.
Caution is advised with sulfonylureas due to potential cross‑reactivity in people with sulfonamide sensitivity.
Digoxin absorption may be affected by sulfasalazine and clinical monitoring is reasonable when co‑prescribed.
Recommended tests are baseline CBC, LFTs and renal function with repeat checks at 2–4 weeks and then approximately every three months.
| Interaction | Practical advice |
|---|---|
| Methotrexate / Azathioprine | Increased haematologic risk — ensure frequent blood monitoring |
| Warfarin | Monitor INR when starting or stopping salazopyrin |
| Sulfonylureas | Check for cross‑reactivity in allergy history |
Storage and handling
Storage conditions, shelf life, special handling and travel
Store salazopyrin at around 25°C with permitted excursions between 15–30°C and keep the container tightly closed.
Protect tablets from moisture and light and advise patients to keep packs in original containers until use.
For rare liquid formulations emphasise accurate dosing and the need to shake if instructed by the manufacturer.
When travelling keep medication in carry‑on luggage and avoid prolonged exposure to heat.
Advise patients to carry a copy of their prescription or a prescriber letter when travelling abroad.
Expired or unwanted medicine should be returned to a pharmacy for safe disposal rather than being thrown away at home.
Do’s and don’ts
- Do store at room temperature and avoid damp places such as bathrooms.
- Do carry medicine in hand luggage when flying.
- Don’t expose tablets to excessive heat or humidity.
Travel checklist
Carry prescription letter, original packaging and keep medication with you in carry‑on luggage.
Formulations and brands
Immediate-release versus delayed‑release
Sulfasalazine is most commonly available as 500 mg tablets in immediate‑release and as 500 mg delayed‑release EN‑tabs.
EN‑tabs are enteric‑coated and often better tolerated for gastrointestinal side effects which can improve adherence.
Brand options include Salazopyrin and Salazopyrin EN‑tabs, or generic sulfasalazine.
Packaging is typically blister packs of tablets.
When choosing between products consider tolerability and patient preference for tablet size.
| Brand | Formulation | Packaging / notes |
|---|---|---|
| Salazopyrin | Immediate‑release 500 mg | Blister packs; established brand |
| Salazopyrin EN‑tabs | Delayed‑release 500 mg | Enteric‑coated, improved GI tolerability |
| Generic sulfasalazine | Immediate or delayed 500 mg | Various manufacturers; pack size varies |
- EN‑tabs Pros: better GI tolerability, useful if nausea limits adherence.
- Immediate‑release pros: widely available.
Counselling points
Checks before starting and counselling points
Before dispensing confirm the indication, recent monitoring blood tests and allergy history, particularly to sulfonamides or salicylates.
Ensure pregnancy status is discussed where relevant and advise patients to speak with their prescriber if they are planning a pregnancy.
Key counselling points include taking salazopyrin with food and a full glass of water, splitting daily doses, expected onset for RA of up to 12 weeks and reversible urine discoloration.
Advise what to do for a missed dose and when to stop and seek urgent medical review.
Checks before starting
- Confirm recent CBC/LFT/renal tests and record dates.
- Check allergy history for sulfonamides/salicylates.
- Review concomitant warfarin, methotrexate or azathioprine therapy.
Switching and alternatives
How to switch between mesalazine/methotrexate and patient counselling points
Mesalazine (Asacol, Pentasa) is often preferred for ulcerative colitis in patients with sulfonamide allergy and has fewer systemic effects.
Methotrexate, leflunomide and hydroxychloroquine are alternative DMARDs used in rheumatoid arthritis depending on disease activity and tolerance.
Do not stop one DMARD and start another without specialist coordination to plan overlapping therapy and blood monitoring.
For patients intolerant of salazopyrin consider mesalazine for UC or a rheumatology review for alternative DMARDs for RA.
When counselling patients explain the rationale for switching — tolerability, monitoring burden or specialist recommendation.
| Drug | Indication | Pros | Cons |
|---|---|---|---|
| Mesalazine (Asacol, Pentasa) | UC | Fewer systemic effects | May not suit all UC phenotypes |
| Methotrexate | RA, JIA | Effective DMARD | Different monitoring and adverse‑effect profile |
- Switching checklist: liaise with prescriber, confirm blood tests, counsel patient on expected timing of effect and side‑effect differences.
Patient support and adherence tools
Local NHS services, charity support, leaflets and digital reminders
NHS patient leaflets, clinic nurse follow‑up and pharmacist medicine use reviews are practical local support options for people starting salazopyrin.
Condition charities such as Crohn’s & Colitis UK and Versus Arthritis provide specialist information and peer support.
Digital adherence aids like pharmacy apps, SMS reminders and printed dosing calendars help patients manage multi‑dose regimens.
Provide patients with written information on the monitoring schedule, clear side‑effect red flags and contact details for GP and specialist teams.
Refer pregnant patients or those planning pregnancy to preconception rheumatology or gastroenterology services for tailored advice.
- Crohn’s & Colitis UK — patient guides and helplines.
- Versus Arthritis — advice for RA and JIA patients.
- Pharmacy medicine use review — schedule adherence support and blood‑test reminders.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Liverpool | England | 9–21 days |
| Leeds | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Bristol | England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Newcastle Upon Tyne | England | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Southampton | England | 9–21 days |
| Plymouth | England | 9–21 days |