
Uniphyllin
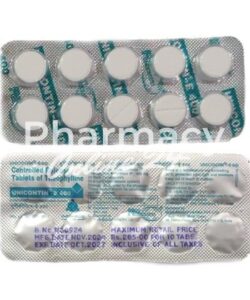
In brief
- In our pharmacy, you can buy Uniphyllin without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Uniphyllin (theophylline) is used for long‑term control of asthma and chronic obstructive pulmonary disease (chronic bronchitis, emphysema). It is a methylxanthine bronchodilator that works mainly as a non‑selective phosphodiesterase inhibitor and adenosine receptor antagonist, increasing intracellular cAMP and relaxing airway smooth muscle; it also has mild central respiratory stimulant effects.
- The usual dose for adults is 300–400 mg of an extended‑release preparation once daily as a starting maintenance dose; the commonly used maximum without serum monitoring is 400 mg/day. Dosing must be adjusted (lower start and careful titration) in the elderly and substantially reduced with liver or kidney impairment; paediatric dosing is by specialist and usually weight‑based.
- Form of administration: oral modified‑release tablets. Swallow extended‑release forms whole — do not crush or chew.
- Onset time: extended‑release preparations typically begin to take effect about 1–2 hours after oral administration (immediate‑release forms act faster, within 15–30 minutes). It is not suitable as a rescue inhaler for acute bronchospasm.
- Duration of action: extended‑release formulations are designed for once‑daily dosing and can provide up to 24 hours of effect; immediate‑release formulations have a shorter duration (around 6–8 hours).
- Alcohol warning: avoid or limit alcohol while taking uniphyllin — alcohol can increase side effects, may affect theophylline metabolism and raise the risk of adverse reactions such as irregular heartbeat and drowsiness.
- The most common side effect is nausea (other frequent effects include vomiting, diarrhoea, headache, restlessness, insomnia, tremor and sweating); serious adverse effects such as rapid/irregular heartbeat or seizures require urgent medical attention.
- Would you like to try Uniphyllin without a prescription?
Legal status and availability in the UK
Uniphyllin (theophylline) is a prescription-only medicine (POM) in the UK.
In our online pharmacy, Uniphyllin is available on prescription, with discreet delivery to the United Kingdom in 9–21 days.
Basic Uniphyllin information
- INN (international nonproprietary name): theophylline
- Brand names available in the United Kingdom: Uniphyllin Continus; generic theophylline modified-release tablets
- ATC code: R03DA04 (respiratory system; drugs for obstructive airway diseases; xanthines)
- Forms and dosages: Modified-release tablets (200 mg, 300 mg, 400 mg)
- Registration status in the United Kingdom: Licensed by the MHRA; prescription-only medicine
- OTC / Rx classification: Prescription-only medicine (POM)
Uniphyllin (theophylline extended-release) remains a niche maintenance bronchodilator in modern UK practice.
Many clinicians favour inhaled corticosteroids and long-acting β2-agonists first, so theophylline tends to be prescribed where inhalers are impractical or adherence is poor.
Typical patient scenarios include homebound elderly people who struggle with inhaler devices, some COPD phenotypes and cases where access to inhaled therapy is limited.
Dosing needs care because steady plasma levels matter; patients may notice tremor or insomnia, and doses should be timed around food (one hour before or two hours after meals).
What Uniphyllin is — active ingredient, class and ATC code
INN, classification and mechanism (concise clinical framing)
What is the active ingredient? The INN is theophylline.
Its pharmacological class is methylxanthine bronchodilator and the ATC code is R03DA04, categorising it among xanthines for respiratory disease.
The primary mechanisms include non-selective phosphodiesterase inhibition and adenosine-receptor antagonism, which together produce modest bronchodilation and stimulant effects on respiratory muscles.
Uniphyllin is intended as a maintenance agent rather than for acute relief, and it is not suitable for immediate rescue treatment of bronchospasm.
Theophylline is a prescription-only medicine in the UK.
Key facts:
- INN: theophylline.
- Class: Methylxanthine bronchodilator (xanthine).
- ATC: R03DA04.
- Brands: Uniphyllin Continus; generic theophylline.
Formulations, strengths and packaging
Tablets and strengths
Uniphyllin is supplied as modified-release tablets to maintain stable plasma concentrations. Tablet strengths include 200 mg, 300 mg and 400 mg.
Label advice states “do not crush or chew; swallow whole”.
Store at room temperature (15–30°C), protected from moisture and heat, in the original packaging.
Indications and typical regimens in practice
When prescribers choose Uniphyllin and starting doses
When is theophylline chosen? It is indicated for maintenance therapy of asthma, chronic bronchitis and emphysema (COPD) particularly where inhaled routes are inadequate or as an adjunct to inhaled agents.
Adult initiation for extended-release preparations commonly starts at 300–400 mg once daily.
Maximum standard dosing without serum monitoring is generally capped at about 400 mg/day for adults aged 16 years and older.
Paediatric use is formulation-dependent and some modified-release products are not recommended for children; specialist weight-based dosing applies where oral solutions or paediatric formulations are used.
For elderly patients and those with comorbidities, begin at a lower dose (for example around 300 mg/day) and titrate slowly while checking plasma concentrations.
Dosing summary:
| Group | Typical start dose | Max without monitoring |
|---|---|---|
| Adults (≥16 years) | 300–400 mg once daily (ER) | 400 mg/day |
| Adolescents (12–15 years) | Specialist dosing (mg/kg) | 16 mg/kg (max 400 mg/day) |
| Children | Not recommended for certain SR brands; specialist dosing | Varies by formulation |
Serum theophylline monitoring is needed before upward titration in maintenance therapy.
Administration guidance and practical tips for patients
How to take Uniphyllin safely for best effect
Take Uniphyllin on an empty stomach — one hour before or two hours after meals — and swallow the tablets whole; do not crush or chew.
Avoid taking the dose within one hour of a particularly fatty meal if the patient is on higher doses, as fatty meals can alter absorption.
If a dose is missed, take it as soon as remembered unless it is near the next scheduled dose; do not double up to make up a missed dose.
Store at room temperature (15–30°C) in the original packaging and protect from moisture and heat.
Uniphyllin is for maintenance and will not relieve an acute wheeze; keep a rescue inhaler available if prescribed.
Dosing adjustments and monitoring
When to change dose and what to check
Theophylline has a narrow therapeutic index so dosing changes commonly require serum level monitoring.
Baseline checks should include liver function, renal function and cardiac history, together with a full review of concomitant medicines that influence CYP1A2 metabolism.
In elderly patients and those with hepatic or renal impairment, start lower and obtain steady-state plasma concentrations before increasing the dose.
Children require specialist mg/kg dosing or an alternative formulation and should be managed by paediatric respiratory teams.
Typical adjustments by group are:
- Children: Not recommended for some SR products; specialist dosing and monitoring required.
- Elderly: Lower starting dose and frequent plasma checks.
- Liver/kidney impairment: Reduce dose substantially and monitor serum levels closely.
Dose changes without monitoring increase the risk of toxicity.
Contraindications and cautions
Absolute and relative contraindications
- Absolute contraindications: Known hypersensitivity to theophylline or other xanthines (for example caffeine or aminophylline); uncontrolled arrhythmias; active peptic ulcer disease.
- Relative cautions: Severe liver disease, congestive heart failure, seizure disorders, hyperthyroidism, elderly patients and other conditions predisposing to tachyarrhythmia.
Drug-interaction risk is high because theophylline is metabolised via hepatic CYP1A2 pathways; many antibiotics and anticonvulsants alter clearance.
Drug interactions — major offenders and management
Common interacting medicines and practical counselling
Theophylline is metabolised mainly by CYP1A2, so clinicians and pharmacists should expect frequent interactions.
Examples of strong inhibitors that raise theophylline levels include ciprofloxacin and some macrolide antibiotics; co-prescription may require dose reduction or extra monitoring.
Enzyme inducers such as carbamazepine, phenobarbital and rifampicin can lower theophylline concentrations, reducing effectiveness.
Counselling should include smoking advice: tobacco smoke induces CYP1A2 and lowers theophylline levels, so stopping smoking commonly increases theophylline concentration and may need dose adjustment.
| Drug/class | Expected effect on theophylline | Action |
|---|---|---|
| Ciprofloxacin, some macrolides | Increase levels (risk of toxicity) | Advise prescriber; request serum level check; counsel patient on toxicity signs |
| Carbamazepine, phenobarbital, rifampicin | Decrease levels (reduced efficacy) | Consider dose increase with monitoring; inform prescriber |
| Smoking | Induces metabolism — lowers levels | Counsel on impact of smoking cessation and arrange monitoring if patient stops smoking |
Contact the prescriber when starting or stopping interacting medicines.
Side effects, toxicity recognition and emergency actions
Common adverse effects vs signs of overdose
Patients often ask what side effects they might feel; common mild to moderate reactions include nausea, vomiting, diarrhoea, headache, restlessness, insomnia, tremor and sweating.
Serious signs associated with toxicity include persistent vomiting, agitation, rapid or irregular heartbeat, seizures and severe headache.
Other biochemical abnormalities reported in severe toxicity include electrolyte disturbances and hypokalaemia.
Seek urgent care for persistent vomiting, new seizures or palpitations, and call 999 or go to A&E for these emergency symptoms.
For mild effects, self-care measures include taking the dose on an empty stomach as instructed, avoiding stimulants such as excessive caffeine and discussing symptom management with the prescriber before making any dose change.
Switching brands, generics and bioequivalence considerations
Practical tips on substitution
Switching between Uniphyllin and generic theophylline products is common in practice.
Check that the formulation type is equivalent (ER/SR) and that the nominal dose matches when substituting; small pharmacokinetic differences between ER products can be clinically relevant.
When plasma monitoring is part of routine care, re-check serum theophylline levels at steady state after any brand change.
Regulatory status in the United Kingdom
Theophylline products are prescription-only in the UK and are dispensed under an NHS or private prescription.
Counselling points
- Take the tablet on an empty stomach, swallow it whole and do not crush or chew it.
- Tell your prescriber about other medicines (especially CYP1A2 interactions), and about cardiac, liver or seizure history.
- Know the common side effects and the emergency signs that need urgent care, such as palpitations or persistent vomiting (call NHS 111, or attend A&E).
- Attend for serum monitoring as planned.
Use in special populations: pregnancy, breastfeeding, paediatrics, elderly, hepatic/renal disease
Practical recommendations and monitoring priorities
Decisions on theophylline use require weighing maternal benefit against potential neonatal or paediatric risks in pregnancy and breastfeeding, and specialist input is recommended.
Paediatric use depends heavily on formulation; some sustained-release products are not recommended for children and dosing should be specialist and weight-based where necessary.
Elderly patients are at higher risk of adverse effects and require lower starting doses with closer serum monitoring due to reduced clearance and interacting comorbidities.
Hepatic or renal impairment slows theophylline clearance, so dose reduction and more frequent plasma concentration checks are essential.
Quick reference FAQs and printable patient summary
Short answers for common queries
Is Uniphyllin a rescue inhaler?
No — it is an oral maintenance bronchodilator and will not relieve an acute asthma attack.
How should I take it?
Take the tablet as directed on an empty stomach, one hour before or two hours after food; swallow whole and do not crush or chew.
Do I need blood tests?
Usually yes for long-term maintenance — serum theophylline levels are required to ensure the dose is safe and effective.
Can I smoke?
Smoking lowers levels by inducing metabolism; quitting can raise concentrations so dose review and monitoring are needed if smoking status changes.
What to do in overdose?
Seek immediate emergency care for persistent vomiting, seizures or arrhythmia — call 999 or attend A&E.
Delivery across the United Kingdom
| City | Region | Delivery time |
|---|---|---|
| London | Greater London | 9–21 days |
| Birmingham | West Midlands | 9–21 days |
| Manchester | Greater Manchester | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Leeds | West Yorkshire | 9–21 days |
| Liverpool | Merseyside | 9–21 days |
| Bristol | South West | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Sheffield | South Yorkshire | 9–21 days |
| Newcastle Upon Tyne | North East | 9–21 days |
| Nottingham | Nottinghamshire | 9–21 days |
| Leicester | Leicestershire | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |

