Plaquenil
In brief
- In our pharmacy, you can buy Plaquenil without a prescription, with delivery in 9–21 days throughout the United Kingdom; usually supplied as 200 mg film‑coated tablets in blister packs or bottles, discreet packaging available.
- Plaquenil (hydroxychloroquine) is used to treat and prevent certain forms of malaria and as a disease‑modifying treatment for rheumatoid arthritis and systemic/discoid lupus; it works as an antimalarial and immunomodulator by accumulating in lysosomes (raising pH), interfering with parasite haem metabolism and reducing antigen presentation and toll‑like receptor‑mediated inflammatory signalling.
- Usual dosages: malaria prophylaxis 400 mg once weekly (adults); malaria treatment typically 800 mg initially then 400 mg at 6, 24 and 48 hours; rheumatoid arthritis and lupus 200–400 mg daily (maximum 400 mg/day); paediatric dosing is weight‑based (e.g. ~6.5 mg/kg for prophylaxis, 3–7 mg/kg/day for chronic use, max 400 mg).
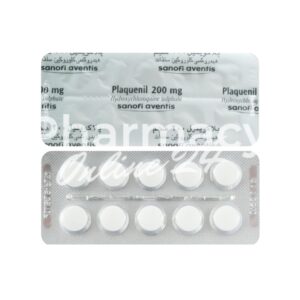
- Form of administration: oral tablets (film‑coated tablets, most commonly 200 mg, available in blister packs of 30 or 60 or in prescription bottles).
- Onset time: for autoimmune conditions clinical benefit usually appears after 1–2 months; for malaria prophylaxis protective effect requires starting 1–2 weeks before exposure; for malaria treatment symptomatic improvement is often within 24–48 hours.
- Duration of action: hydroxychloroquine has a long terminal half‑life (weeks to months, typically ~40–50 days), so effects and drug levels persist for weeks after stopping; chronic autoimmune therapy is continued for months to years as needed.
- Alcohol warning: avoid excessive alcohol intake — alcohol can worsen liver injury risk and gastrointestinal side effects; discuss alcohol use with your clinician, especially if you have liver disease.
- The most common side effec is gastrointestinal upset (nausea, vomiting, abdominal cramps); other common effects include headache, dizziness and skin rash; long‑term use carries a risk of retinal toxicity so regular eye monitoring is essential.
- Would you like to try Plaquenil without a prescription?
Basic Plaquenil information
- INN (international nonproprietary name): Hydroxychloroquine
- Brand names available in the United Kingdom: Plaquenil; generic hydroxychloroquine sulfate
- ATC code: P01BA02
- Forms and dosages: film-coated tablets 200 mg, in blisters of 30 or 60
- Manufacturers in the United Kingdom: Sanofi (Plaquenil)
- Registration status in the United Kingdom: Prescription-only medicine (POM); Plaquenil is authorised for use in the UK
- OTC / Rx classification: Prescription-only medicine (POM)
Legal status and availability in the UK
Plaquenil (hydroxychloroquine) is a prescription-only medicine (POM) in the UK. Long-term treatment is usually arranged by the GP following specialist input, with repeat prescriptions.
In our online pharmacy, Plaquenil is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Product overview: formulation, INN and branding
International nonproprietary name (INN) and ATC
Hydroxychloroquine is the International Nonproprietary Name (INN) for the active substance in Plaquenil and its equivalents.
The ATC code for hydroxychloroquine is P01BA02, classifying it among antiparasitic agents as an aminoquinoline antiprotozoal.
The drug is supplied mostly as hydroxychloroquine sulfate or hydroxychloroquine, depending on the label, so always verify the exact wording on pack labels.
Brand names, form and common packaging
Plaquenil (Sanofi) is the most widely recognised brand and is commonly dispensed as 200 mg film-coated tablets.
Generic products are labelled hydroxychloroquine sulfate. Plaquenil is supplied as 200 mg film-coated tablets in blister packs of 30 or 60.
Verify whether the label lists hydroxychloroquine sulfate or hydroxychloroquine, and confirm the tablet imprint and strength.
Indications and typical use
Licensed indications
Hydroxychloroquine is used in the treatment and prevention of certain forms of malaria where appropriate.
It is licensed as a disease-modifying antirheumatic drug (DMARD) for rheumatoid arthritis.
Hydroxychloroquine is an established treatment for systemic lupus erythematosus (SLE) and discoid lupus.
Off-label and discouraged uses
Off‑label uses do occur in clinical practice, but high‑profile off‑label use for COVID‑19 is not supported by consistent evidence and is discouraged.
Patients should discuss any off‑label proposals with their specialist prescriber.
Authorised indications:
- Treatment and prevention of malaria in appropriate regions and strains.
- Rheumatoid arthritis as a DMARD.
- Systemic and discoid lupus erythematosus.
Common off‑label uses that require caution:
- COVID‑19 treatments are discouraged due to lack of reliable evidence.
- Some dermatological indications beyond discoid lupus may be used by specialists with appropriate monitoring.
Dosing
Typical adult regimens
For malaria prophylaxis the standard adult dose is 400 mg once weekly, starting 1–2 weeks before travel and continuing for 4 weeks after return.
Malaria treatment regimens include an initial 800 mg dose followed by 400 mg at 6, 24 and 48 hours, with weight adjustments as required.
For autoimmune disease such as RA or SLE maintenance dosing is typically 200–400 mg daily, given as a single dose or divided dose according to tolerance and prescriber advice.
Weight- and renal-based adjustments
| Indication | Adult dose | Paediatric guidance | Typical duration |
|---|---|---|---|
| Malaria prophylaxis | 400 mg weekly | 6.5 mg/kg up to 400 mg | Start 1–2 weeks before, continue 4 weeks after |
| Malaria treatment | 800 mg then 400 mg at 6, 24, 48 hrs | Weight-adjusted; max total ~2 g | 3-day regimen |
| RA / SLE | 200–400 mg daily | 3–7 mg/kg/day (max 400 mg) | Often long-term; monitor for efficacy/safety |
Doses above 5 mg/kg actual body weight carry a higher retinal risk and need specialist review.
Counselling points for patients:
- Take with food to reduce gastrointestinal upset.
- If you miss a dose, take it when remembered unless it is near the next dose — do not double up.
- Paediatric dosing must be calculated by a specialist; do not attempt to divide adult tablets for children without instruction.
Safety profile, absolute contraindications and practical checks
Absolute contraindications
Known hypersensitivity to hydroxychloroquine or other 4‑aminoquinolines is an absolute contraindication to prescribing or dispensing hydroxychloroquine.
Pre‑existing retinopathy is an absolute contraindication to starting hydroxychloroquine.
The full-strength tablets are not recommended in very small children under six years due to overdose risk.
Checks before supply
- Known hypersensitivity: the medicine is not supplied; the prescriber is contacted for alternatives.
- Pre-existing retinopathy: supply is held until the prescriber or ophthalmology confirms.
- Young children (under 6 years): specialist dosing is needed; adult tablets are avoided.
- Tell your pharmacist or prescriber about heart conditions, severe liver or kidney disease, G6PD deficiency, pregnancy or breastfeeding, and your eye screening history.
- Seek urgent care for acute visual or cardiac symptoms.
Side effects: everyday tolerability and red flags
Common mild–moderate effects
Most patients report mild gastrointestinal symptoms such as nausea, vomiting, abdominal cramps and diarrhoea when starting hydroxychloroquine.
Headache and dizziness are reported and often settle with continued use or dose adjustment.
Mild skin rashes and long‑term changes such as brown skin hyperpigmentation or nail changes are described with prolonged therapy.
Taking tablets with food and splitting doses can reduce gastrointestinal side effects in some patients.
Serious adverse effects
Rare but serious adverse effects include progressive retinal toxicity with visual field defects and blurred vision, and cardiac effects such as QT prolongation and arrhythmias.
Severe cutaneous adverse reactions and life‑threatening cardiac events are uncommon but require immediate action.
What to do:
- Stop the medicine and seek urgent medical attention for acute vision changes.
- Seek immediate care for syncope, palpitations or severe allergic reactions.
- Report suspected adverse reactions to the Yellow Card scheme and inform the prescribing clinician.
Monitoring requirements: eyes and heart
Recommended eye screening schedule
A baseline ophthalmic assessment is recommended before or shortly after starting long‑term hydroxychloroquine.
Annual screening is advised after five years of treatment for most patients, with earlier screening when risk factors are present.
High‑risk factors requiring earlier or more frequent screening:
- Doses over approximately 5 mg/kg actual body weight.
- Renal impairment.
- Concurrent tamoxifen therapy.
- Pre‑existing retinal disease.
Cardiac monitoring and ECG considerations
Assess history of conduction disorders, heart failure and any concurrent QT‑prolonging drugs before supply.
Consider ECG monitoring or prescriber review if the patient is symptomatic or is starting new interacting medicines such as macrolide antibiotics.
Pharmacists should prompt prescribers to check electrolytes and consider cardiology review when multiple cardiac risk factors are present.
Record monitoring dates on medication records and remind patients to attend scheduled ophthalmology appointments.
Drug interactions and co-prescribing safety
High-risk combinations to avoid or monitor
Hydroxychloroquine can prolong the QT interval and therefore increases arrhythmia risk when combined with other QT‑prolonging agents.
Notable interactions include azithromycin, certain antiarrhythmics (class I and III), some antipsychotics and methadone.
Hydroxychloroquine should not be combined with other 4‑aminoquinolines.
Practical pharmacist actions (checks and counselling)
Run interaction checks on the PMR and the BNF for co‑prescribed medicines and recent prescriptions.
If a potentially dangerous interaction is found, contact the prescriber to recommend ECG monitoring, electrolyte checks or alternative therapy.
For patients on warfarin, advise closer INR monitoring as hydroxychloroquine may affect anticoagulation in some cases.
Document all communications and counsel patients to report palpitations, syncope or new cardiac symptoms immediately.
Special populations: pregnancy, breastfeeding, children, elderly
Pregnancy and lactation practical guidance
Pregnancy and lactation require specialist input when considering hydroxychloroquine use.
Guidance notes that hydroxychloroquine is generally avoided unless the prescriber judges that maternal benefit outweighs risk.
Discuss any pregnancy or breastfeeding plans with the prescribing specialist and document the rationale for continued therapy if used.
Paediatric and elderly considerations
Paediatric dosing is strictly weight‑based, typically 3–7 mg/kg/day with a maximum of 400 mg daily, and must be calculated by a specialist.
Tablet formulation and the risk of accidental overdose in young children mean special handling and secure storage are essential.
Elderly patients have higher retinal and cardiac risk profiles and should have renal function reviewed and dose adjustments made where indicated.
Storage, transport and safe disposal
Storage and travel advice
Store hydroxychloroquine at room temperature between 15–30°C, away from moisture and light.
Keep the medicine out of reach of children because overdose can be fatal in small children.
For travel, carry medication in original packaging and keep prescriber or hospital letters handy for customs or medical queries.
Disposal and child safety measures
Return unwanted or expired tablets to a pharmacy medicine take‑back scheme for safe disposal; do not flush medicines down the toilet or sink.
When dispensing, advise patients about childproof storage and how to inspect blister packs for tablet discolouration or odour that may indicate deterioration.
Alternatives and switching
Alternative antimalarials and DMARDs
For malaria, alternatives include chloroquine in susceptible areas and artemisinin derivatives where resistance is present.
For autoimmune diseases alternatives to hydroxychloroquine include methotrexate, sulfasalazine, leflunomide and biologic DMARDs depending on disease severity and patient factors.
Practical switching notes and pharmacist role
Switching from hydroxychloroquine to another DMARD should be coordinated with the specialist prescriber, with attention to washout or overlap requirements and additional monitoring such as liver function tests for methotrexate.
Pharmacists should reconcile repeat prescriptions, provide clear dispensing instructions during transition and counsel patients on the risk of disease flare if treatment is stopped abruptly.
Document all changes and confirm monitoring plans with the prescriber to ensure safe transition between therapies.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Leeds | England | 9–21 days |
| Liverpool | England | 9–21 days |
| Bristol | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Newcastle | England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Norwich | England | 9–21 days |
Final practical tips for patients
If you collect hydroxychloroquine from a community pharmacy, bring any hospital letters and recent test results to speed supply and confirm monitoring arrangements.
Check the tablet imprint and strength (200 mg is most common) when you receive your pack and ask the pharmacist if anything looks different.
Keep a reminder for annual ophthalmology checks after five years of therapy or sooner if you have risk factors such as high dose or renal impairment.
Report any worrying symptoms immediately.